What the anion gap Measures
The anion gap is a computed value used to assess electrolyte balance and support assessment of acid-base status. It helps clinicians interpret a laboratory result by calculating the difference between recorded cations and recorded anions in the blood. Because routine chemistry panels do not measure every charged particle, the anion gap offers insight into unmeasured anions that may be present during a metabolic disturbance.
An anion gap calculator is a helpful diagnostic tool for examining blood chemistry quickly. It is especially valuable when a patient has an electrolyte imbalance, since small shifts in sodium, chloride, bicarbonate, and related values can suggest an underlying acid-base disorder. In simple terms, the calculation helps identify whether the blood has an excess of acids, an excess loss of base, or a pattern that reflects electrolyte shift physiology.
The anion gap is not a diagnosis by itself. It is part of broader acid-base analysis and should be interpreted alongside the full electrolyte panel, the serum bicarbonate level, and other clinical findings. Used well, it turns a basic chemistry snapshot into a more helpful picture of acid-base balance.
How the chloride shift Influences the Anion Gap
The chloride shift describes the shift of ions that works to preserve electroneutrality in body fluids. In clinical interpretation, alterations in chloride often occur in response to alterations in bicarbonate. When bicarbonate falls, chloride may rise to maintain stability, which can keep the anion gap near normal even when an acid-base disorder is present.
This relationship is important because the chloride shift can obscure or reveal a metabolic problem. For example, if bicarbonate is lost through the kidneys or gastrointestinal tract, the body may preserve or raise chloride. The result is a pattern of normal anion gap acidosis, also called hyperchloremic acidosis. In this setting, the anion anion gap in chronic kidney disease gap may not rise, even though the patient has clear metabolic acidosis.
By contrast, if acids accumulate and bicarbonate falls without a matching chloride increase, the anion gap rises. That pattern is more suggestive of high anion gap acidosis. Understanding the chloride shift helps distinguish whether the chemistry reflects a gain of acids, a reduction in buffer, or a compensatory change in the buffer system.
For that reason, an anion gap calculator is especially helpful when reviewing chloride level changes. It helps relate the raw numbers to the underlying physiology and improves recognition of a true anion deficit versus a straightforward compensatory shift.
Anion Gap Formula and Calculator Inputs
The standard anion gap calculation uses sodium, potassium, chloride, and bicarbonate. Many clinicians apply the streamlined formula:
Anion gap = Sodium − (Chloride + Bicarbonate)Some versions include potassium as well:
Anion gap = (Sodium + Potassium) − (Chloride + Bicarbonate)Both methods reflect the relationship between measured cations and anions. The calculator input values generally come from common serum electrolytes or a chemistry panel. Because each lab may report somewhat different units or reference intervals, the exact reference range should always be interpreted in context.
In practical use, the calculator relies on accurate values for:
- Sodium, the principal measured cation Potassium, in some cases included in the formula Chloride, a major measured anion Bicarbonate, often reported as CO2 on chemistry panels
These numbers show the patient’s current blood chemistry and help estimate whether there are excess unmeasured anions contributing to the result. A helpful way to think about the calculation is that it estimates the gap left behind by anions not listed directly on the panel.
When used properly, the anion gap calculator provides a quick diagnostic calculation that assists with bedside decision-making. However, it should always be reviewed as part of the full clinical picture rather than treated as a standalone answer.
Normal Ranges and Corrected Anion Gap
A typical normal anion gap changes a bit by laboratory procedure and whether potassium is added. Many clinicians view as a value around 8 to 12 mEq/L normal when potassium is omitted, though the specific range should correspond to the lab’s reference range. A normal result does not always eliminate illness; it may simply show that the electrolyte pattern is balanced in a way that does not raise the gap.
Albumin is a key unmeasured anion and has a strong effect on the anion gap. When albumin is low, the measured anion gap may look falsely normal or low even if acids are present. This is why albumin correction matters so much in interpretation. In hypoalbuminemia, the corrected value can uncover hidden metabolic problems that the unadjusted number fails to show.
A corrected value calculates what the anion gap would be if albumin were normal. This is valuable because low albumin reduces the anion contribution from the protein fraction, creating an apparent anion deficit. Without adjustment, a patient with serious acid retention may look less abnormal than they truly are.
Albumin correction is very important in hospitalized patients, malnutrition, liver disease, or inflammation, where hypoalbuminemia is common. In these settings, the corrected value gives improved clinical interpretation than the raw number alone. It can also help avoid missing a mixed acid-base disorder.
Elevated Anion Gap vs Typical Anion Gap Disorders
Acid-base acidosis is the general category most often reviewed with the anion gap. The main distinction is whether the gap is increased or remains normal. A high anion gap acidosis implies that acids or acid equivalents have accumulated, increasing the amount of unmeasured anions in the blood.
Common causes of high anion gap acidosis include lactic acidosis, ketoacidosis, and renal failure. In each case, the body is keeping or producing acids faster than they can be cleared or buffered. The anion gap rises because bicarbonate is consumed while accompanying anions remain present in circulation.
A normal anion gap acidosis, on the other hand, usually reflects bicarbonate loss with a corresponding rise in chloride. This is where the chloride shift becomes clinically relevant. The chloride increase helps preserve electroneutrality, but the tradeoff is a lower bicarbonate concentration and a persistent acidosis without a widened gap.
Identifying the difference matters because the causes and treatment strategies differ. High-gap disorders often prompt evaluation for toxic ingestion, tissue hypoxia, or severe metabolic crisis. Normal-gap disorders more often suggest gastrointestinal bicarbonate loss, renal tubular problems, or other patterns of chloride-related compensation.
Understanding Outputs in Medical Settings
This anion gap should be interpreted alongside the overall presentation, instead of in isolation. An arterial blood gas helps show whether the patient has acidosis, alkalemia, or a combined disorder. Meanwhile, serum electrolytes indicate whether shifts in chloride, bicarbonate, or sodium explain the gap.
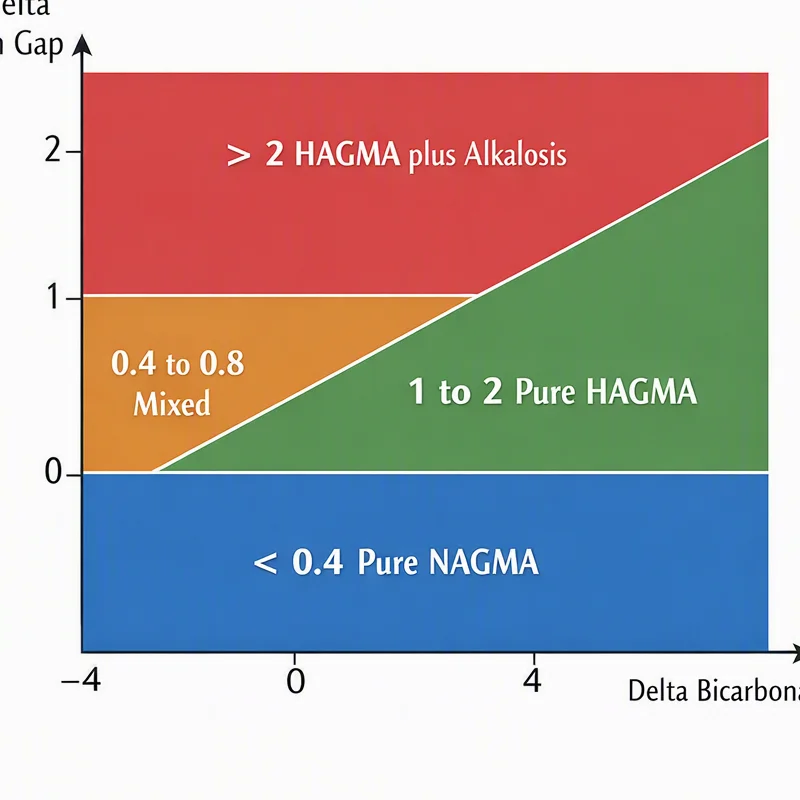
One useful concept is the delta gap, which contrasts the increase in anion gap to the fall in bicarbonate. It can help detect mixed acid-base problems. For example, if the gap is elevated above expected, there may be an additional metabolic alkalosis or chronic respiratory process. If the change is lower than expected, there may be a concurrent normal-gap acidosis.
Clinical interpretation becomes more accurate when the anion gap is viewed as part of a broader acid-base analysis. A patient may have a high-gap metabolic picture on chemistry results, but the arterial blood gas may demonstrate compensation, overlap, or a second process. That is why the anion gap calculator should aid, not replace, clinical reasoning.
When reviewing a serum bicarbonate result, it is also important to note whether the bicarbonate drop corresponds to the chloride rise. If chloride is elevated while bicarbonate is low, the pattern may support a normal anion gap acidosis. If chloride is not elevated and bicarbonate is low, an accumulation of acids is more likely.
Frequent Causes of Irregular Findings
Unexpected anion gap results often indicate a specific metabolic disorder. A elevated gap may reflect lactic acidosis, ketoacidosis, renal failure, or exposure to toxins. These conditions increase acid load or decrease acid clearance, which increases anion concentration from unmeasured acids.
Lactic acidosis usually develops when tissue oxygen delivery is impaired or when metabolism switches toward anaerobic pathways. Ketoacidosis may occur in diabetes, starvation, or alcohol-related states. Renal failure impairs the kidney’s ability to excrete acids and regenerate bicarbonate, resulting in a gradually increasing gap over time.
Normal-gap abnormalities are often linked to gastrointestinal loss of bicarbonate, such as diarrhea, or renal causes that lose bicarbonate. In these situations, chloride goes up to replace the lost base, which stops the anion gap from widening. That makes the chloride shift a major clue in separating acid loss from acid accumulation.
Some toxins can also produce unusual patterns or mixed disorders. Because toxin-related states may evolve quickly, a single calculator result should not be used in isolation. Instead, it should be interpreted with the patient’s symptoms, medication exposures, renal function, and the full electrolyte panel.
Constraints of an Anion Gap Calculator
An anion gap calculator is useful, but it has limitations. One important issue is laboratory variation. Various analyzers and reporting methods can alter the reference range, especially when potassium is included or omitted. A result that appears abnormal in one scenario may be acceptable in another.
Measurement error can also skew the outcome. Slight inaccuracies in sodium, chloride, or bicarbonate may shift the gap enough to affect interpretation. This is particularly important when values are near the cutoff or when a patient has unusual body chemistry, such as severe dehydration, marked protein abnormalities, or mixed acid-base states.
One more drawback is that the calculator does not determine the source of the problem. It can show that the numbers point to an acid-base issue, but it cannot tell whether the issue is lactic acidosis, ketone acidosis, kidney insufficiency, poison exposure, or loss of bicarbonate. It requires history, examination, and additional testing.
Because of these factors, clinical judgment is still essential. The calculator works best as a support tool for medical interpretation, not a substitute for complete evaluation. When results do not fit the patient’s condition, recheck the entered values, check the specimen, and review the broader context.
Frequently Asked Questions About Anion Gap and Chloride Shift
What is an anion gap calculator used for?
An anion gap calculator is used to determine the gap methanol toxicity and anion gap between measured cations and anions in blood tests. It aids evaluate acid-base balance, detect possible metabolic acidosis, and guide assessment of an acid-base disorder using results such as sodium, chloride, and bicarbonate.
How does chloride shift affect the anion gap?
The shift in chloride can help offset bicarbonate loss by elevating chloride, which may keep the anion gap normal even when acidosis is present. That is why a pattern of rising chloride with decreasing bicarbonate often indicates normal anion gap acidosis, while a gap rise without chloride replacement suggests a raised-gap process.
What’s the normal anion gap range?
The normal anion gap is influenced by the lab and whether potassium is included in the formula. A lot of labs use a range around 8 to 12 mEq/L, but the exact reference range should consistently match the local method and reporting format.
Why do albumin levels change the anion gap?
Albumin is a major unmeasured anion, so low albumin lowers the measured gap. In hypoalbuminemia, the raw result may fail to reflect the true acid load, which is why albumin correction is critical for accurate interpretation.
When should a high anion gap be considered urgent?
A high gap may be urgent when it is associated with severe symptoms, rapid breathing, altered mental status, shock, or suspected lactic acidosis, ketoacidosis, renal failure, or toxins. In those settings, prompt evaluation with arterial blood gas, serum electrolytes, and full clinical assessment is important.