Understanding the Anion Gap?
The anion gap is a practical way to assess the balance of ions in the blood. It is based on standard electrolytes measured on a basic lab test, especially sodium, chloride, and bicarbonate. Because routine testing does not measure every charged particle directly, the anion gap acts as an approximate estimate of the discrepancy between measured cations and measured anions.
In practical terms, the anion gap helps clinicians evaluate acid-base balance and identify hidden acids or other causes of a metabolic disorder. It is often used as a diagnostic tool during laboratory interpretation of serum electrolytes, especially when a patient’s chemistry panel points to metabolic acidosis.
The concept represents an electrochemical difference in anion concentration. Since not all unmeasured ions are included in routine testing, the gap can indicate what is happening beyond the standard panel. A higher-than-expected value often points to extra acids in the blood, while a lower value may suggest less common issues such as protein changes or lab variation.
An electrolyte panel or broader serum chemistry panel usually provides the values used for this estimate. That is why the anion gap is widely used in clinical evaluation and patient assessment: it gives fast insight into possible metabolic acidosis causes without requiring specialized testing first.
How the Anion Gap Calculator Operates
An anion gap calculator carries out the anion gap calculation mechanically using values from serum chemistry. The traditional anion gap formula is:
anion gap = sodium - (chloride + bicarbonate)Some versions of the calculation may include potassium, but most clinical use relies on the more basic form above. The calculator is designed to make the calculation easy and minimize arithmetic mistakes when reviewing lab results.
To use the tool, you provide the measured sodium, chloride, and serum bicarbonate values from the lab report. The calculator then takes away the sum of chloride and bicarbonate from sodium and shows the result. Because the inputs come directly from standard electrolytes, the result is straightforward to connect to the patient’s serum bicarbonate level and the broader acid-base picture.
This kind of lab result analysis is especially useful when trying to separate routine abnormalities from patterns that suggest a more serious disorder. The anion gap does not provide a diagnosis by itself, but it causes of HAGMA helps frame the differential diagnosis and directs next steps in test interpretation. In many cases, it is one of the first numbers reviewed after a chemistry panel is available.
The calculator is also useful because it standardizes anion gap calculation across different settings. Even when the basic formula is the same, different laboratories may have slightly different methods, assays, or reference range values. A calculator helps place the number in context rather than treating it as a standalone answer.
Interpreting High Anion Gap Results
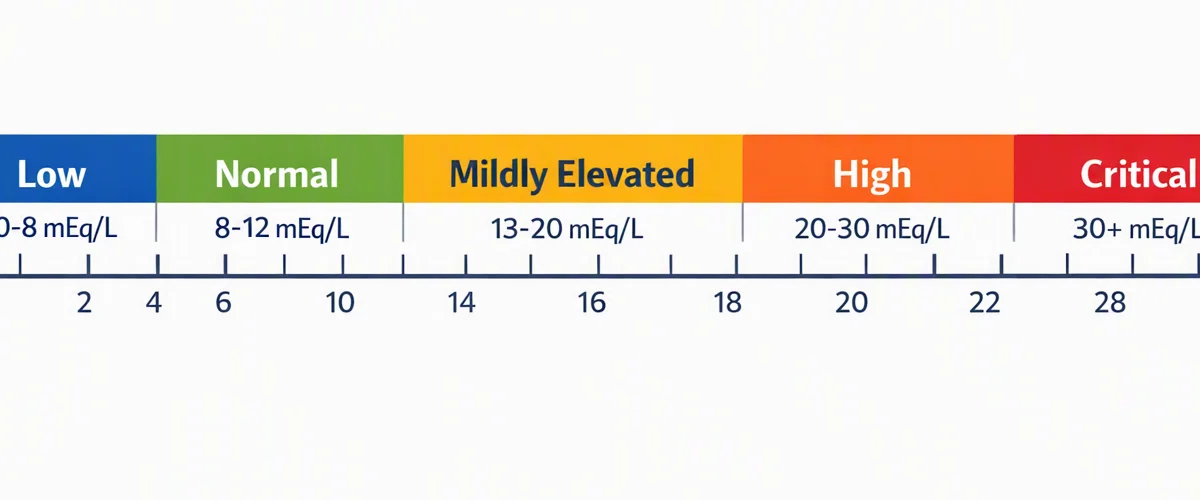
A elevated anion gap usually points toward acid-base acidosis, particularly when the bicarbonate level is low. In this setting, the body has stored excess acids or depleted base, and the gap increases because those excess acids are not directly measured in the standard panel.
Reading the result depends on the normal range used by the lab and the rest of the lab values. A mildly elevated number may be less concerning if there is a clear explanation, while a clearly abnormal result often requires a more careful review of the patient’s history, symptoms, and other labs. The same value can mean different things depending on the clinical situation.
It helps to think of the anion gap as a clue rather than a diagnosis. A high value supports the presence of an acid load from one of several sources, but it does not identify the exact cause. That is why the result should be paired with the rest of the chemistry panel, and often with a blood gas if the acid-base status is not fully clear.
Main considerations for interpretation include:
- High anion gap with low bicarbonate often suggests metabolic acidosis. A normal value does not rule out all acid-base problems; it may indicate a normal anion gap process instead. Changes in albumin can alter the apparent gap and affect comparison to the lab’s reference range. Timing matters, because acid-base patterns can shift quickly during illness or treatment.
In real-world clinical evaluation, the result should be read alongside symptoms, medication history, kidney function, and the full chemistry profile. The calculator is a practical entry point, but it is only one part of careful patient assessment.
Typical Causes of a elevated anion gap
The main causes of a high anion gap are states that increase acid formation or reduce acid clearance. These classic categories include lactic acidosis, ketoacidosis, renal failure, and exposure to certain toxins. Each one leads to accumulation of acids or unmeasured anions, which increases the gap.
Lactic acidosis occurs when lactate rises faster than the body can clear it. This can happen during poor tissue oxygen delivery, severe infection, shock, or other states of stress. Because lactate is an unmeasured anion in standard labs, the anion gap often increases.
Ketoacidosis is another leading cause. It may occur when the body breaks down fat rapidly and creates acidic ketones. This is often seen in uncontrolled diabetes, but it can also occur with prolonged fasting, heavy alcohol use, or other metabolic states. The calculator can help identify this pattern early when bicarbonate is falling and the gap is worsening.
Renal failure can also result in a high gap because the kidneys are less able to remove acids. As acid retention progresses, the chemistry panel may show multiple abnormalities. The anion gap may help differentiate advanced kidney-related acid buildup from other forms of acidosis.
Toxins are another important category. Certain ingestions or exposures can trigger a significant acid-base disturbance, often with a rising anion gap. In these situations, the calculator can signal clinicians to a serious metabolic process that needs prompt evaluation.
Additional less common causes may exist, but these four categories cover many of the most important metabolic acidosis causes. The key point is that a high value should prompt a broader search for the source of excess acid rather than being interpreted in isolation.
Corrected Anion Gap and Albumin Review
A single of the most important details in anion gap assessment is the effect of albumin. Albumin is a negatively charged protein, so when its level is low, the measured gap may appear lower than expected. This is why clinicians may use a corrected anion gap when hypoalbuminemia is present.
The concept behind correction for albumin is easy to understand: if albumin is reduced, some of the “missing” negative charge is already gone, and the gap can underestimate the true burden of unmeasured acids. Adjusting the number helps bring the result closer to the appropriate reference range for that patient.
Why does this matter? A patient with low albumin may have a deceptively normal or only mildly elevated gap even when a serious acid-base problem is present. Without adjustment, the interpretation may miss a high anion gap process or understate its severity. The corrected value improves lab result analysis and helps align the number with the actual clinical picture.
Using albumin adjustment is especially helpful when the chemistry panel and symptoms do not seem to match. If the numbers suggest a mild abnormality but the patient looks much sicker than expected, the corrected anion gap may reveal a clearer signal. This is one reason the anion gap calculator is best viewed as part of a broader diagnostic tool set rather than a single fixed answer.
Keep in mind that the exact correction method may vary by institution. The practical goal is not to replace the original result, but to interpret it more accurately in the presence of altered protein levels. That makes albumin an important part of thoughtful acid-base review.
When to Consider Medical Review
A high anion gap is a lab result, but it can reflect a potentially serious underlying illness. Medical evaluation is essential when the result occurs with concerning symptoms such as rapid breathing, confusion, severe nausea, vomiting, dehydration, weakness, or reduced responsiveness. These symptoms may suggest marked metabolic stress or worsening acidosis.
Urgent emergency care may be needed when a patient has severe illness, abnormal breathing, altered mental status, chest pain, or signs of shock. In these situations, the anion gap calculator can be useful, but it should never delay direct treatment or rapid clinical assessment.
A blood gas test is often used when the acid-base problem needs closer evaluation. It can show pH, carbon dioxide, and the degree of acidosis more directly than a routine chemistry panel. When combined with the electrolyte panel, it helps confirm the severity of the disorder and guides management.
In general, a concerning result should be reviewed in context:
- Look at the full electrolyte panel, not just one number. Check whether bicarbonate is low and whether there is a clear metabolic acidosis. Consider kidney function, medication use, and possible toxin exposure. Use the corrected anion gap if hypoalbuminemia is present.
If the lab pattern is unexpected, or if the patient appears ill, prompt medical attention is appropriate. The calculator is a support tool for decision-making, not a substitute for direct evaluation.
FAQ
What is a normal anion gap?
A typical anion gap varies by the testing method and the reported normal range. In many settings, the expected result lies within anion gap in chronic kidney disease a fairly tight range on the chemistry panel. Since methods differ, it is best to check the result with the specific lab’s stated range rather than relying on a single universal number.
How is the anion gap calculated?
The fundamental anion gap formula is sodium less chloride plus bicarbonate. Simply put, anion gap = sodium - (chloride + bicarbonate). This is the most widely used anion gap calculation used by an anion gap calculator and is based on routine serum chemistry results.
What does a high anion gap mean?
A high anion gap often suggests metabolic acidosis from excess unmeasured acids in the blood. Frequent sources include lactic acidosis, ketoacidosis, renal insufficiency, and certain toxins. The value should be assessed with the remaining results of the labs and the patient’s symptoms.
Why is albumin used to correct the anion gap?
Albumin is a key negative-charged protein in blood, so low levels can make the gap look falsely low. The corrected anion gap compensates for hypoalbuminemia and offers a more accurate picture of the patient’s acid base status. This enhances test interpretation when the chemistry pattern does not fully fit the clinical picture.
What disorders can lead to a high anion gap metabolic acidosis?
High anion gap metabolic acidosis may result from a number of key conditions, especially lactic acidosis, ketoacidosis, renal failure, and certain toxins. These disorders increase unmeasured acids and change the pattern on the electrolyte panel. A thorough clinical evaluation and often a blood gas help identify the exact cause.