How the Anion Gap Evaluates
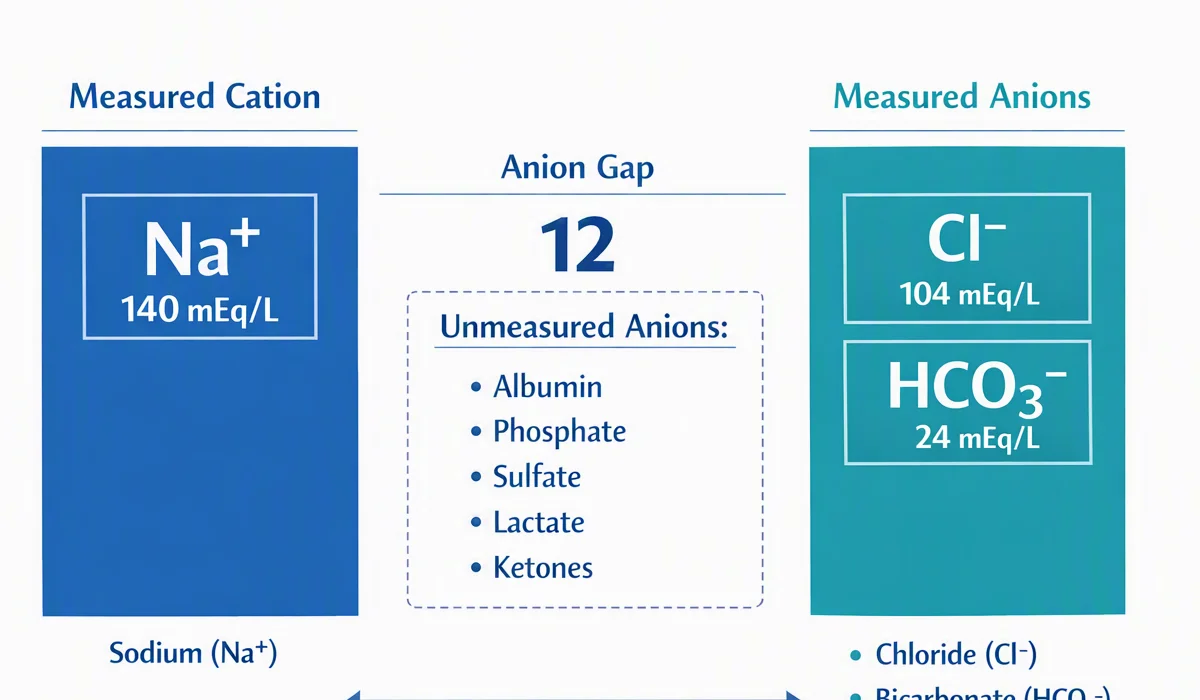
The anion gap is a calculated value that assists clinicians analyze electrolytes and detect indicators of metabolic acidosis. It represents the balance between measured cations and measured anions in the serum chemistry panel, mainly using sodium, chloride, and bicarbonate. Because not all charged particles are directly measured, the anion gap provides indirect insight into unmeasured anions and broader acid-base disorders.
In practical terms, an elevated or reduced anion gap can support clinical assessment when reviewing an electrolyte panel. It supports acid-base interpretation by helping clinicians see whether the body is retaining acids, losing bicarbonate, or dealing with another metabolic derangement. This makes the anion gap especially useful in laboratory interpretation, where small patterns can point toward important diagnoses.
The concept is straightforward: the gap estimates the difference between what is measured and what is expected in the bloodstream. When the balance shifts, the result can signal an electrolyte imbalance or a disorder that needs more focused evaluation. In that sense, the anion gap serves as a quick form of diagnostic support that fits naturally into a larger diagnostic workflow.
How to Use an Anion Gap Calculator
An anion gap calculator is a useful resource for rapid calculation during emergency evaluation, ward review, or internal medicine consultation. It helps clinicians record key lab values and obtain an answer without manual arithmetic, decreasing the chance of error during busy decision-making. Most calculators rely on sodium, chloride, and serum bicarbonate, and some also permit inclusion of potassium.
To use the calculator, input the patient’s measured lab values from the chemistry panel. The result can then be compared with the expected reference interval or local reference range. A value outside the usual range may lead to further clinical assessment for metabolic acidosis, a hidden acid load, or a relevant electrolyte abnormality.
Including potassium is optional in many settings. Some formulas leave out it because potassium is present in much lower concentration than sodium, but other clinicians favor the potassium-inclusive version for a more complete picture of anion concentration. What matters most is consistency: use the same method when trending results over time.
The calculator is most helpful when combined with the rest of the chart. For example, if the serum bicarbonate is low, the anion gap can help separate a true high-gap process from a normal-gap disorder. If the pattern is unexpected, the calculator becomes part of a broader laboratory interpretation approach rather than a stand-alone answer.
Anion Gap Formula and Common Variations
The typical anion gap formula is typically written as:
anion gap = sodium − (chloride + bicarbonate)
If potassium is included, the formula becomes:
anion gap = sodium + potassium − (chloride + bicarbonate)
These equations estimate the gap between measured positive and negative ions in the blood. The outcome gives a useful screen for hidden acids and other unmeasured anions. In many clinical settings, the potassium-free formula is anion gap in chronic kidney disease favored because it is simpler and widely used in routine serum chemistry reporting.
A corrected anion gap is often required when albumin is abnormal. Albumin Go here is a major unmeasured anion, so low albumin can make the apparent gap look falsely normal or low. This is why albumin correction is crucial when interpreting results in patients with malnutrition, chronic illness, liver disease, or inflammation.
The idea of a normal anion gap depends on the assay used by the laboratory and the local reference range. Different analyzers and methods can yield slightly different values, so clinicians should read the result in context rather than rely on one universal cutoff. A calculator that incorporates the correct laboratory method enhances diagnostic support and lowers misclassification.
Understanding Increased Anion Gap Values
A raised result usually suggests high anion gap metabolic acidosis. With this pattern, the body has retained acids that are not directly assessed on the chemistry panel, causing the calculated gap to rise. This finding frequently signals clinically important metabolic acidosis and requires prompt attention, especially when seen with symptoms, hemodynamic instability, or worsening mental status.
One major cause is lactic acidosis, where lactate accumulates because of tissue hypoperfusion, sepsis, hypoxemia, seizures, or severe physiologic stress. Another common cause is ketoacidosis, which may arise in diabetes, starvation, or alcohol-related illness. In both cases, the calculator helps quantify the acid-base pattern and enhances faster clinical decision support.
Renal failure is another classic contributor. When kidney function declines, acids are retained and normal buffering capacity is reduced. The result can be a increasing anion gap along with other changes in the metabolic profile. In these cases, the calculator helps distinguish kidney-related acid retention from other causes of acid-base disorders.
High-gap results should always be interpreted with the full clinical picture. A single number does not diagnose the underlying disorder, but it can strengthen the case for urgent risk stratification, additional labs, blood gas testing, and a focused review for toxic exposures, ischemia, or severe dehydration. Used this way, the calculator becomes a useful part of clinical assessment rather than just a mathematical tool.
Reviewing Normal or Reduced Anion Gap Results
A normal-gap metabolic acidosis often indicates loss of bicarbonate or impaired acid handling without a major rise in unmeasured acid compounds. Frequent examples include gastrointestinal bicarbonate loss and certain renal tubular problems. Here, the calculator remains valuable because a normal gap can sharpen the differential rather than ending the evaluation.
A reduced anion gap is not as frequent, but it should not be ignored. The most frequent explanation is hypoalbuminemia, since reduced albumin lowers the pool of unmeasured anions. This can mask a clinically important disturbance if the result is not adjusted with a proper corrected anion gap. In patients with chronic disease or poor nutritional status, albumin correction is often essential.
Another important cause is testing error. Sample problems, analyzer issues, contamination, or transcription mistakes can produce misleading results. If the number does not fit the clinical picture, repeat testing is appropriate before making major decisions. A low or unexpectedly normal result should also prompt review of the overall electrolyte pattern and the patient’s acid-base status.
Because the anion gap is derived from measured values, small analytic differences can have a greater effect than expected. This is why clinicians should compare the number against the laboratory’s reference range and review trends over time. A normal gap does not always mean the patient is stable, and a low value can sometimes be the earliest clue to a broader laboratory or physiologic issue.
Medical Decision Support Applications
The anion gap is a useful component of clinical decision support because it converts everyday chemistry data into usable information. In emergency medicine, it assists promptly detect serious patients with unexplained metabolic acidosis. In critical care, it enables serial monitoring of acid-base status and assists track response to treatment over time.
For instance, a patient with altered mental status, hypotension, or tachypnea may have a hidden acid-base problem that is not clear from the chart alone. A fast anion gap calculator result can inform the next step in the workup process, whether that means reviewing lactate, ketones, kidney function, or a blood gas. This is where the tool delivers genuine diagnostic support rather than basic educational value.
In routine inpatient care, the calculator can aid distinguish whether a falling bicarbonate reflects a high-gap process or a normal anion gap disorder. That distinction matters because it guides the differential diagnosis and determines what further workup is needed. When integrated into daily review of the electrolyte panel, the calculator supports more reliable laboratory interpretation and more secure decision making.
The anion gap is also useful in risk stratification. A rising gap may signal worsening illness even before symptoms become pronounced. Likewise, a low or corrected-normal value can allay concerns clinicians that the apparent disorder is not as severe than it first appeared, provided the rest of the assessment is concordant.
Drawbacks, Common Errors, and Recommended Practices
One important limitation involves albumin correction. Since albumin is a major unmeasured anion, low levels can obscure an elevated gap. When correction is skipped, the clinician may underestimate the severity of the disorder. Always check albumin when the anion gap seems out of line with the patient’s presentation.
A further trap is overreliance on a single reference range. Various laboratories use different analyzers and reporting conventions, so a result should be interpreted in the context of the local assay. What looks abnormal in one lab may be normal in another. For that reason the best practice is to combine the calculator with the laboratory’s own reporting framework.
A mixed acid-base disorder can also make harder interpretation. A patient may have both a high-gap process and a second disturbance that partially offsets it, making the bicarbonate or pH seem less abnormal than expected. In these cases, the calculator is only one part of the analysis and should be paired with blood gas data, clinical context, and serial trends.
Repeat testing is appropriate when the result conflicts with the clinical picture or when there is concern for laboratory error. Rechecking the chemistry panel can avoid misclassification and unnecessary treatment. Best practice is to review sodium, chloride, bicarbonate, potassium, and albumin together, then interpret the result within the broader picture of acid-base disorders and the patient’s overall condition.
The best results come from using the anion gap as part of a structured review: confirm the lab values, assess albumin, consider the reference range, and then connect the pattern to the likely diagnosis.
FAQs About the Anion Gap Calculator
What is an anion gap calculator used for?
An anion gap calculator is used to support clinical decision support by rapidly estimating the anion gap from routine lab values. It helps clinicians assess metabolic acidosis, spot possible unmeasured acids, and organize the differential for acid-base disorders. It is especially helpful during chart review, emergency assessment, and ongoing laboratory monitoring.
How do you calculate the anion gap from lab values?
The most common anion gap formula is sodium − (chloride + bicarbonate). Some versions also include potassium, using sodium + potassium − (chloride + bicarbonate). The calculator uses the patient’s lab values from the chemistry panel to perform a quick, reliable gap calculation.
Why do you correct the anion gap for albumin?
You correct the anion gap for albumin because albumin is a major unmeasured anion. If albumin is low, the measured gap may look artificially normal or low. A corrected anion gap gives a more precise picture of the true acid-base status, especially in patients with hypoalbuminemia.
What does a high anion gap mean clinically?
A high result suggests high anion gap metabolic acidosis, which often reflects accumulation of acids such as lactate or ketones. Common causes include lactic acidosis, ketoacidosis, and renal failure. The finding should prompt more clinical evaluation rather than be interpreted in isolation.
Can a normal anion gap still indicate a serious disorder?
Yes. A normal anion gap can still occur in significant illness, including normal anion gap metabolic acidosis. It may also be seen when a high-gap process is masked by hypoalbuminemia or when a mixed disorder is present. That is why clinicians should consider the full clinical context, the serum bicarbonate, and the possibility of laboratory error before concluding the evaluation.