An Anion Gap Calculator is a handy tool for fast lab review, assisting you interpret electrolyte patterns and detect an acid-base imbalance that may need care. In standard review, the anion gap is especially useful because it turns a standard electrolyte panel into a more meaningful clinical clue. By looking at sodium, chloride, and bicarbonate collectively, you can evaluate acid-base balance and identify possible metabolic imbalance earlier.
This calculation is not meant to take the place of clinical judgment. Rather, it supports interpretation of lab values in the right clinical context. For many patients, especially during routine review of a basic metabolic panel or comprehensive metabolic panel, the anion gap offers a quick way to sort abnormal findings and determine whether follow-up is needed.
What the anion gap shows in routine metabolic analysis
The anion gap is a derived value based on common electrolytes measured in standard testing. It reflects the gap between positive and negatively charged ions in the blood, using the main lab measurements most clinicians already assess. The core components are sodium, chloride, and bicarbonate.
In basic terms, the anion gap helps estimate whether there are unmeasured acids or other charged particles affecting the blood chemistry. That is why it can serve as a diagnostic clue during routine review. A normal result does not exclude every problem, but it can help focus the evaluation when a patient has symptoms or abnormal lab values.
The calculation is often used as part of an electrolyte panel to support screening for metabolic acidosis. It is not a standalone diagnosis. Instead, it provides another layer to the overall assessment of acid-base balance, especially when electrolyte trends vary over time.
A useful way to think about the anion gap is that it helps show whether the body is “missing” measured negative ions or whether extra acids are present. That makes it helpful for routine review, follow-up, and quick evaluation of abnormal chemistry results.
Using an anion gap calculator step-by-step
An Anion Gap Calculator is straightforward to use when you know the right calculator inputs. Most tools need the values for sodium, chloride, and bicarbonate. Others include albumin entry so the result can be modified for albumin correction.
The basic anion gap formula is typically: The basic formula is usually:
Anion gap = sodium - (chloride + bicarbonate)
For the calculation in order:
- Locate the patient’s electrolyte values on the lab report. Enter sodium, chloride, and bicarbonate into the calculator. Review the calculated anion gap. Compare the result with the lab’s reference range or reference interval. If albumin is low, evaluate whether an albumin correction is needed.
When using the calculator, watch units and lab method. Small differences in reporting can affect the final measurement. As a result, the result should always be interpreted together with the patient’s overall picture, not in isolation.
If albumin is included, the calculator may produce an adjusted result. This is particularly helpful because low albumin can mask an elevated anion gap. A quick adjusted calculation can enhance detection during routine review and help reveal a more accurate metabolic pattern.
Normal, increased, and decreased anion gap values
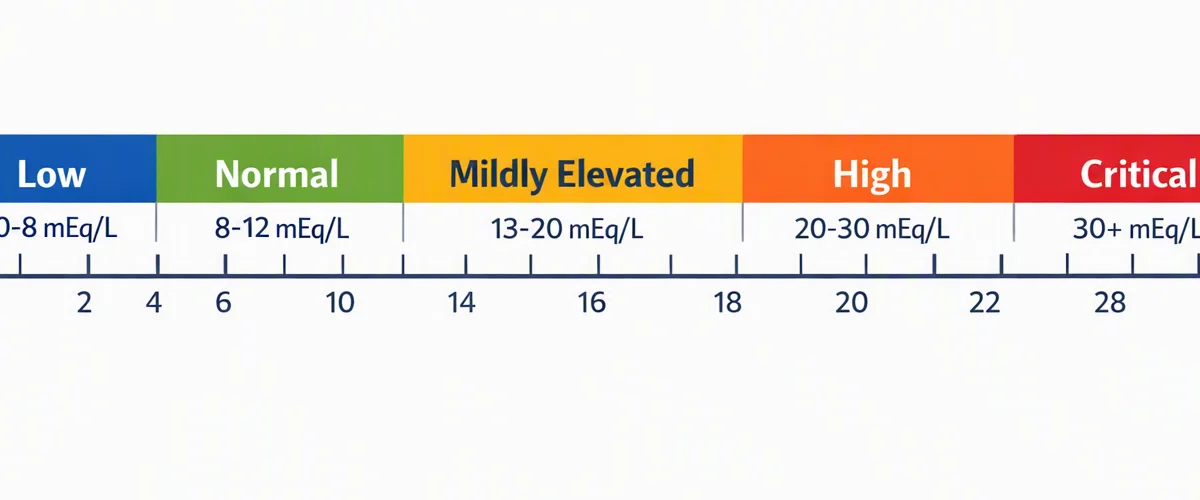
A expected anion gap often indicates that the measured electrolytes are in a balanced state, though this does not mean that everything is fine. The expected reference range may differ from one laboratory to another because of laboratory variation in procedures and interpretation.
A high anion gap metabolic acidosis is the primary abnormal finding many clinicians watch for. It indicates that unmeasured acids are piling up, which can be an serious sign of a metabolic problem needing additional review. This is one of the most important reasons the anion gap is included in standard lab review.
A low anion gap is uncommon but still relevant. It may indicate lab artifact, low albumin, or other changes affecting charge balance. Because the calculation depends on measured electrolytes, a low value should trigger a careful check for reporting issues and more complete clinical interpretation.
It is important to note that laboratory variation can affect whether a value is considered typical, mildly abnormal, or clearly abnormal. One lab’s threshold may differ slightly from another’s. That is why using the local reference range matters more than relying on a one universal number.
In everyday practice, the main value of the anion gap is pattern recognition. A normal value may be reassuring in some settings, while a high value may point toward a more urgent acid-base disorder. A low value may be a clue to review the sample, consider albumin, or review the full chemistry profile.
Typical causes of an abnormal anion gap
When the anion gap is abnormal, the best next step is to look for patterns rather than isolated numbers. In routine review, a number of common conditions can explain an elevated or reduced result. The clinical question is whether the pattern fits the patient’s symptoms, history, and other lab values.
Lactic acidosis is a classic cause of elevated anion gap. When lactate builds up, it contributes to metabolic acidosis and shifts the electrolyte relationship. This is often seen in situations involving poor tissue oxygen delivery, severe illness, or other stress states.
Ketoacidosis is another important cause. In this setting, ketone bodies increase acid load and push the anion gap higher. This pattern can appear in uncontrolled diabetes, prolonged fasting, or other metabolic states where the body burns fat for fuel.
Renal failure can also produce a high anion gap because the kidneys are less able to remove acid effectively. As acid retention increases, the calculation may reflect a broader metabolic disturbance. This makes the anion gap a helpful fast-check tool during chemistry review.
Hypoalbuminemia is a common explanation for a low or misleading result. Since albumin is a major negatively charged protein, a drop in serum albumin can lower the measured gap. This is why albumin should always be part of the interpretation when the result seems unexpected.
Other causes can include medications, toxin exposure, or shifts in the way ions move across compartments. A chloride shift may occur as the body tries to maintain electrical neutrality, changing the relationship between measured electrolytes. Even when the cause is not obvious, the anion gap can still shape the next step in evaluation.
Correcting the anion gap for albumin
Because albumin contributes significantly to the body’s unmeasured anions, albumin correction is often needed for a more precise interpretation. This is especially true when the patient has decreased serum albumin. Without adjustment, the anion gap may appear normal even when an acid-base problem is present.
The concept behind the correction is easy to understand: if albumin is reduced, the measured anion gap may be falsely decreased than expected. An adjusted anion gap accounts for that change and gives a better estimate for clinical interpretation. This can improve assessment in routine lab review, especially when the numbers do not seem to fit the patient’s condition.
Albumin matters because of protein binding and its role as an unmeasured anion. When serum albumin falls, the balance of measured ions changes. The correction helps restore context to the calculation and improves the quality of the clinical interpretation.
For practical use, albumin correction is most helpful when there is marked hypoalbuminemia or when an otherwise suspicious lab pattern is not explained by the unadjusted result. In those cases, an adjusted calculation may reveal occult metabolic acidosis or support a clearer threshold for concern.
Even when a calculator performs the correction on its own, it remains important to understand what the adjustment means. The corrected value is not a independent diagnosis. It is a better measurement for estimating the real acid-base pattern in https://anion-gap-review424.quillnesty.com/posts/anion-gap-calculator-in-mmol-l-formula-range-and-meaning context.
How anion gap calculation integrates into regular laboratory review
The anion gap is most useful when it is part of a wider review of the basic metabolic panel or comprehensive metabolic panel. Such panels provide the raw data that make the calculation possible. In routine lab review, the anion gap can turn a standard chemistry set into a more informative snapshot of acid-base status.
Clinicians often use the result to screen for hidden problems, show that an abnormal electrolyte pattern makes sense, or decide whether further assessment is needed. That is why the anion gap is valuable not just for emergencies, but also for routine review and follow-up. It adds context to the overall clinical interpretation of lab values.
For example, if bicarbonate is low and sodium and chloride are changing in a predictable way, the anion gap can help determine whether the pattern fits a high-gap process or a normal-gap process. That distinction matters because it alters the direction of the evaluation.
The anion gap is also useful during trend review. A single number can be informative, but comparing results over time often gives a more complete picture of whether a metabolic issue is improving, stable, or worsening. This is one reason the calculation remains a key part of routine chemistry assessment.
In practical terms, the best use of the anion gap is to support efficient decision-making. It can highlight abnormal findings that deserve attention, but it should always be reviewed with the full electrolyte panel, symptoms, and clinical context.
Next steps after using the anion gap
After using the calculator, your next step is not simply to call the result as within range or out of range. Good interpretation starts with asking whether the value aligns with the rest of the labs and the patient’s presentation. If it does not, you may need additional details before making a decision.
Repeat may be appropriate when the value is unexpected or appears inconsistent with the clinical findings. It can help exclude collection issues, laboratory variability, or short-term changes. Since testing variation can influence the result, a repeat measurement may clarify whether the abnormality is genuine.
An arterial gas analysis can assist when the acid-base picture is not clear or a more extensive assessment is needed. A venous gas analysis may also be useful in many situations and can provide additional detail without requiring arterial sampling. Either test can support deeper assessment of acid-base status.
Most importantly, use clinical assessment. Anion gap is only one finding among many, and it should match the patient’s symptoms, history, and other findings. If the result suggests acidosis or another major metabolic imbalance, the follow-up should be guided by the overall clinical picture.
When the result is abnormal, the following step may involve checking medications, hydration status, kidney function, glucose, lactate, or ketones. When the result is normal, but there is still concern, consider whether albumin adjustment or repeat evaluation is needed. In short, the calculator helps with initial screening, but interpretation is what turns the number into action.
Frequently asked questions about anion gap results
What is anion gap calculator used for?
An Anion Gap Calculator is used to quickly compute the anion gap from standard lab values and assist with interpretation of electrolyte results. It supports with evaluating for metabolic acidosis, checking acid-base balance, and identifying patterns that may require follow-up in routine review.
What is a normal anion gap interval?
The reference range for a typical anion gap varies with the lab and technique used. That means there is not one universal number. Always compare the result to the lab-specific normal range listed by the lab and take into account laboratory variation when reviewing the result.
Why do you adjust the anion gap for albumin?
You use albumin adjustment because low albumin level can make the anion gap look lower than it truly is. Since albumin contributes to the body’s negative charge through protein binding, an corrected anion gap can offer a more reliable measurement and support clinical interpretation.
What causes a high anion gap?
A elevated anion gap is commonly associated with lactate acidosis, ketone acidosis, and kidney failure. These conditions add to unmeasured acids and often lead to elevated anion gap metabolic acidosis. The result should always be reviewed with the full clinical context and other lab values.
Can a normal anion gap still mean a problem is present?
Yes. A standard result does not rule out all disease. Some patients may have hyperchloremic metabolic acidosis, or the abnormality may be masked by hypoalbuminemia. That is why the anion gap should be considered alongside the rest of the basic chemistry panel, the comprehensive metabolic panel, and the overall clinical interpretation.