What the Anion Gap Indicates
The anion gap is a computed value used in lab interpretation to help judge acid-base balance and detect patterns that may indicate a specific acid-base disorder. It is derived from common electrolytes in the electrolyte panel, especially sodium, chloride, and bicarbonate. In practical terms, an anion gap calculator helps calculate the difference between measured positively charged and negatively charged ions, serving as a quick diagnostic aid for clinicians and lab readers.
The concept is based on electrical neutrality: the body’s fluids must keep a balance between cations and anions. Because some ions are not routinely measured, the anion gap reflects the presence of these unmeasured anions. This makes it a useful screening tool for metabolic conditions that alter serum sodium, serum chloride, and serum bicarbonate.
In everyday clinical interpretation, the anion gap is most often used to evaluate suspected metabolic acidosis. It can help distinguish high-gap acidosis from normal-gap acidosis, support the interpretation of a broader metabolic derangement, and support faster lab result analysis. While the number itself is simple, its meaning depends on the full clinical picture, including the patient’s acid-base status.
How to Use an Anion Gap Calculator
An anion gap calculator typically requires three core lab values: sodium, chloride, and bicarbonate. They are typically reported on a routine metabolic panel or similar electrolyte panel. After input, the calculator uses the anion gap formula to produce a result that can be compared with the expected reference range or reference interval.
To use it properly, first confirm that the values are from the same sample and are current. Then enter the serum sodium, serum chloride, and serum bicarbonate exactly as reported. The calculator will subtract chloride and bicarbonate from sodium to estimate the gap. This is a simple approach to support clinical interpretation, but the result should always be reviewed alongside other labs and symptoms.
Because the anion gap is only one part of lab result analysis, it should not be interpreted in isolation. Changes in bicarbonate often reflect acid loss or acid buffering, while shifts in chloride may suggest compensatory changes. If the value is abnormal, the next step is usually to consider whether the pattern fits a metabolic acidosis, whether a corrected value is needed, and whether an arterial blood gas is delta gap online tool available to clarify acid-base status.
Anion Gap Formula and Variants
The classic formula for the anion gap is:
Anion gap = sodium - (chloride + bicarbonate)
Certain clinicians also include potassium in the calculation. In this variant, the formula becomes:
Anion gap = sodium + potassium - (chloride + bicarbonate)
The majority of modern lab systems and bedside references use the version without potassium because potassium is a lesser component of extracellular charge and adds limited value in many routine settings. However, understanding both forms can help when comparing historical reports or different clinical references.
The value is also influenced by albumin, which is a major negatively charged protein in plasma. Since albumin contributes to the measured gap, low albumin can make the result appear falsely low. For this reason, albumin correction is important in many cases, especially when evaluating a patient with suspected acidosis or significant illness. A corrected anion gap can reveal abnormalities that a raw value might hide.
Overall, the anion gap formula is straightforward, but the interpretation is nuanced. A calculator helps speed up the arithmetic, while the clinician’s job is to decide whether the number is consistent with the overall acid-base picture.
Expected Anion Gap Values and Interpretation
The anticipated reference range for the anion gap varies by laboratory method, analyzer, and whether potassium is included. This is why the laboratory-specific reference interval is important more than any single universal cutoff. Many labs report a range that is tighter or more expansive depending on assay design, so the same result may be within range in one setting and slightly abnormal in another.
A high anion gap suggests extra unmeasured acids in the blood, while a low anion gap can indicate either a reduction in unmeasured anions, an increase in unmeasured cations, or a problem with the test itself. In practical terms, the anion gap is a signal rather than a diagnosis. It guides the next steps in clinical interpretation.
Interpretation should also factor in the context of acid-base balance. A mildly abnormal value may be less worrisome if other labs are stable, while a pronounced deviation may suggest a serious metabolic derangement. The same number can mean varied things depending on the patient’s hydration status, kidney function, and overall acid-base status.
For this reason, the anion gap is best viewed as a screening tool that aids broader decision-making rather than as a stand-alone result.
Sources of Elevated Anion Gap
An elevated anion gap often points to high anion gap metabolic acidosis, a condition in which acids build up and raise the difference between measured cations and anions. Common causes include lactic acidosis, ketoacidosis, and renal failure. These conditions add to unmeasured anions, which increases the calculated value.
Lactic acidosis occurs when lactate accumulates faster than it can be cleared, often in settings of poor perfusion, severe illness, or impaired oxygen delivery. Ketoacidosis develops when ketone bodies collect, such as in uncontrolled diabetes, starvation, or alcohol-related metabolic stress. In both cases, the extra acid consumes bicarbonate, decreasing serum bicarbonate and widening the gap.
Renal failure can also cause elevation because the kidneys cannot efficiently excrete acid load and metabolic byproducts. As kidney function worsens, retained acids contribute to metabolic acidosis. In real-world lab interpretation, this pattern may appear alongside changes in creatinine, blood urea nitrogen, and other markers of impaired clearance.
Other contributors to a high gap may include toxins or less common metabolic disorders, but the most frequent clinical causes remain lactic acidosis, ketoacidosis, and renal failure. An anion gap calculator helps identify the pattern quickly, but the next step is always to align the result with the patient’s symptoms and additional tests.
Reasons of Decreased Anion Gap
A reduced anion gap is less common and can be missed, but it may also be clinically meaningful. A leading cause is hypoalbuminemia, because albumin is a negatively charged protein that typically contributes to the gap. When albumin drops, the anion gap may appear reduced even if the patient has an underlying acid-base problem.
Paraproteinemia is an additional cause. In disorders that generate abnormal proteins, the balance of measured and unmeasured ions can shift, reducing the result. This is why a persistently low anion gap should prompt thought about protein abnormalities as well as the broader clinical context.
Laboratory error is also a regular explanation. An unusual result should always raise the possibility of a specimen problem, analyzer issue, or transcription mistake. Because the anion gap depends on several measured values, a small measurement error in sodium, chloride, or bicarbonate can change the final number.
When the number is unusually low, it is useful to recheck the raw labs, review the reference interval, and consider whether hypoalbuminemia or paraproteinemia explains the finding. In some cases, the apparent abnormality goes away once the data are retested or adjusted.
Adjusted Anion Gap and Albumin Correction
The corrected anion gap accounts for the effect of albumin on the measured result. Since albumin is a major unmeasured anion, low levels can mask a true elevation. That is why albumin correction is especially useful in patients with low protein states, chronic illness, inflammation, or fluid overload.
A common correction formula modifies the observed anion gap upward when albumin is below normal. While exact equations may vary by institution, the general idea is simple: lower albumin means a higher corrected value than the raw calculation suggests. This helps uncover hidden acid accumulation that might otherwise be missed during routine lab result analysis.
Hypoproteinemia can also affect interpretation, because the total protein environment shifts along with albumin. In such cases, a low uncorrected gap may not reflect true normality. The corrected value provides a more reliable view of acid-base balance and supports more accurate clinical interpretation.
For patients with suspected metabolic acidosis and low albumin, correction is often essential. Without it, the clinician may underestimate the severity of a high-gap acidosis. The corrected value is not a replacement for the full evaluation, but it is a valuable step in interpreting the chemistry panel.
How to Read Results in Acid-Base Conditions
The anion gap is most useful when considered alongside the broader assessment of acid-base disorder. In suspected acidotic metabolic state, the first question is whether the gap is elevated. If it is, the pattern suggests elevated anion gap metabolic acidosis. If the gap is normal but bicarbonate is low, the pattern may fit non-anion gap metabolic acidosis, sometimes called non-gap acidosis.
An arterial gas analysis helps establish the pH, respiratory compensation, and overall acid-base balance. In combination with the chemistry panel, it clarifies whether the problem is primarily metabolic, respiratory, or mixed. The anion gap does not replace the blood gas; it works alongside it.
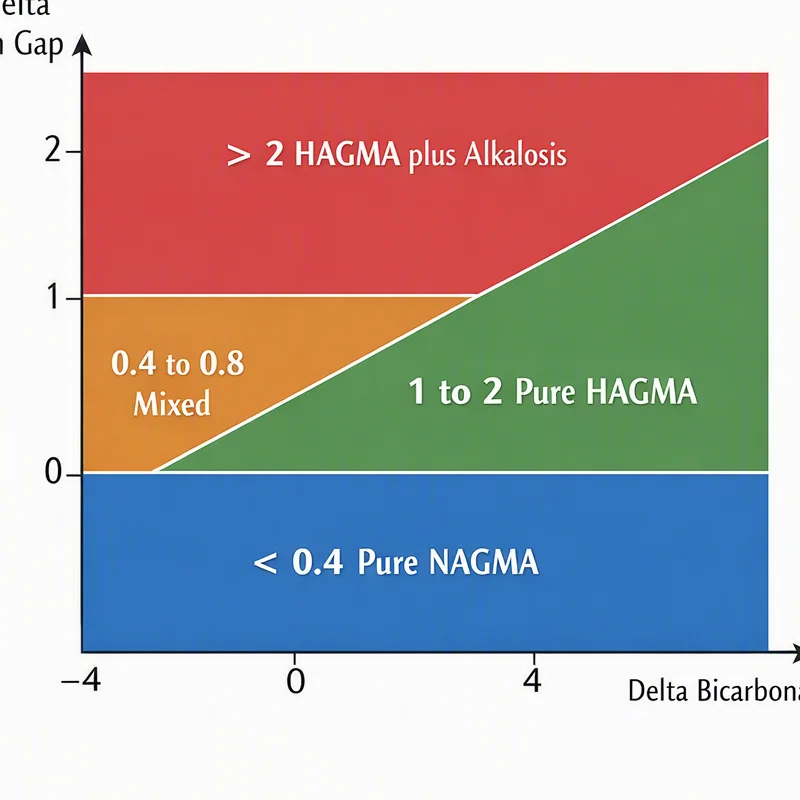
The gap comparison can be helpful when the anion gap is elevated. This approach compares the rise in the anion gap with the fall in bicarbonate to look for mixed disorders. If the change in one does not match the change in the other, a second acid-base process may be present. This is especially useful in more complex presentations where more than one metabolic process is affecting the patient.
In practice, clinicians use the anion gap to move from a general label like metabolic acidosis to a more specific working diagnosis. That is what makes it such a valuable piece of test interpretation.
Typical Errors in Anion Gap Interpretation
One of the most common pitfalls is relying on a single value without considering the full chemistry pattern. A result may appear normal despite a clinically significant problem if there is testing error or if the laboratory’s normal range is different from the one used in a textbook. Be sure to check the lab’s own range before drawing conclusions.
Another issue is failing to account for undetected anions or protein changes. A low albumin level can hide a meaningful elevation, and a normal raw result may not fully reflect the patient’s acid burden. Likewise, paraproteins or other unusual proteins can distort interpretation.
It is also important not to mix up the anion gap with a diagnosis. This value suggests a pattern, but the cause must be identified through history, exam, and additional testing. Missing laboratory error can also lead to unneeded worry or missed treatment.
Good clinical interpretation means reviewing the full set of data: sodium, chloride, bicarbonate, potassium when relevant, albumin, kidney function, and blood gas findings. In this context, the anion gap is a helpful tool; used in isolation, it can mislead.
FAQ About the Anion Gap Calculator
What is an anion gap calculator used for?
An anion gap calculator is used for clinical interpretation of electrolyte results. It helps interpret lab values from the chemistry panel to assess acid-base status, screen for metabolic acidosis, and identify patterns such as high anion gap metabolic acidosis or normal anion gap metabolic acidosis. It is a practical screening tool, not a diagnosis by itself.
How do you calculate the anion gap from lab values?
The basic anion gap formula is sodium - (chloride + bicarbonate). Some versions include potassium, but the classic formula usually does not. The calculator uses the reported serum sodium, serum chloride, and serum bicarbonate to produce the result. Always compare the value with the lab’s reference range.
What causes a high anion gap?
A high anion gap usually reflects extra unmeasured anions and is often seen in high anion gap metabolic acidosis. Common causes include lactic acidosis, ketoacidosis, and renal failure. The result should be interpreted with the full clinical picture, including an arterial blood gas when available.
Why can a low anion gap happen?
A low anion gap can occur with low albumin, paraproteinemia, or testing error. Because albumin affects the gap, low protein levels may cause the value seem lower than expected. If the finding is unexpected, recheck the test and check the rest of the lab values before concluding it is clinically meaningful.
When should albumin correction be applied to the anion gap?
Albumin correction should be applied when albumin is low or when a patient has suspected protein deficiency. In those cases, the uncorrected number may downplay the true gap. A corrected anion gap gives a clearer estimate of the patient’s acid base problem and can expose hidden acid buildup.