An Anion Gap Calculator is a practical method to calculate the anion gap from standard lab data. Using sodium, chloride, and carbon dioxide values from a routine electrolyte panel, it enables clinicians and students quickly evaluate acid-base balance and identify patterns that may point to an underlying metabolic acidosis or other acid-base disorder. Because the calculation comes directly from common serum chemistry results, it is one of the most useful tools in basic laboratory interpretation.
The value is not a diagnosis by itself. Rather, it is a preliminary and interpretation aid that reflects the relationship between measured serum electrolytes and the unmeasured ions in the blood. In practice, this makes the anion gap a useful diagnostic tool for evaluating a result in the context of the patient’s symptoms, history, and other laboratory values.
Explaining the Anion Gap Shows
The anion gap represents the gap between the main measured cations and anions in the blood. It is based on the principle of electroneutrality, which means the body keeps plus and minus charges in check. Since standard chemistry tests do not measure every ion, the gap approximates the amount of unmeasured anions present in the sample.
In routine clinical use, the anion gap is a quick way to determine whether an abnormality in the blood chemistry may indicate an acid-base disorder. A variation in the gap can point to build-up of acids, loss of bicarbonate, or changes anion gap in chronic kidney disease in other charged particles. That is why it is often discussed alongside serum electrolytes and other markers of acid-base balance.
For many patients, the anion gap is most valuable when interpreting a basic metabolic profile or an electrolyte panel. The calculation can provide a fast sense of whether the laboratory pattern is within range or whether further evaluation is needed. It is especially helpful in identifying a possible metabolic disorder that changes the balance of acids and bases.
Calculating Anion Gap from Sodium, Cl, and Carbon Dioxide
The typical Anion Gap Calculator process uses three values: sodium, chloride, and carbon dioxide. In most lab panels, the reported carbon dioxide value is used as a stand-in for bicarbonate. Because bicarbonate is the main measured base in this formula, the carbon dioxide result is essential to the final number.
The simple calculation is:
Anion gap = sodium − (chloride + bicarbonate)
When using a routine lab report, the formula is often written as:
Anion gap = sodium − (chloride + CO2)
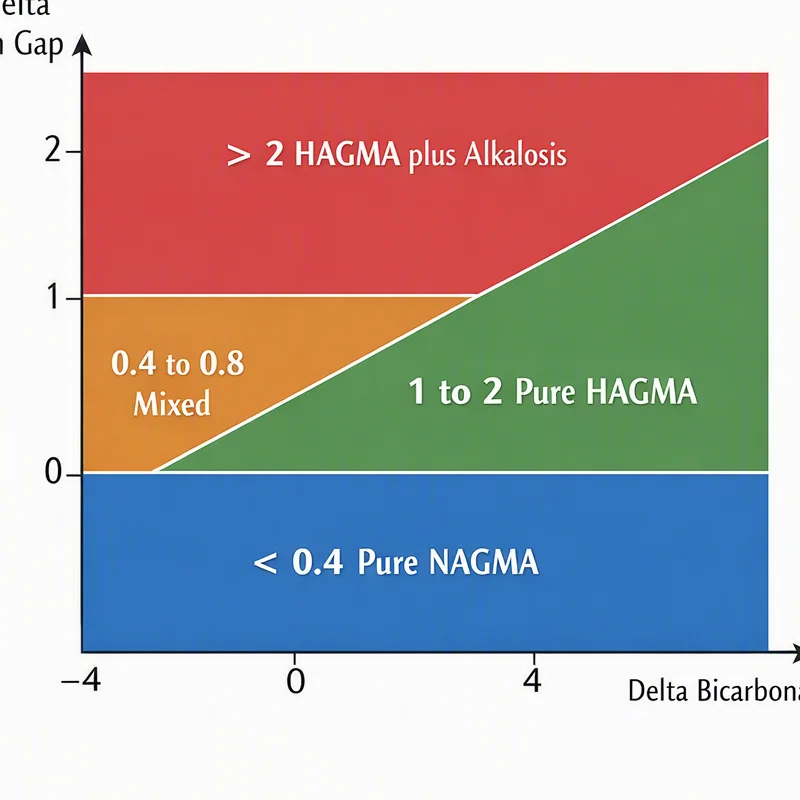
That means the calculator deducts the sum of chloride and carbon dioxide from sodium. For example, if sodium is 140, chloride is 104, and CO2 is 24, the calculation is 140 − (104 + 24) delta ratio for mixed disorders = 12. This is a direct calculation that can be performed without a tool or through an web-based calculator.
The advantage of this method is its speed. Because sodium, chloride, and CO2 are part of a common electrolyte panel, the anion gap can be obtained without additional testing. This makes it useful as a rapid evaluation step during interpretation of routine laboratory values.
Equation, Unit System, and Typical Range
The anion gap formula is often expressed in mEq/L. The unit reflects the charge concentration of the measured ions in serum electrolytes. Most calculators report the answer in the same units because the result is derived from concentrations of charged particles rather than mass or volume.
The exact reference range can vary depending on the laboratory method used. Different analyzers, instruments, and reporting conventions can shift the expected value slightly. Many labs consider a typical anion gap to fall within a range that centers around the low teens, but the important point is to use the local reference interval that matches the testing method.
This is why the same numerical value may be interpreted differently depending on the clinical setting. An anion gap that appears normal on one report might be borderline or mildly abnormal on another if the lab uses a different calibration or calculation approach. A careful review of the report is part of sound medical judgment.
In most cases, the formula is best used as a practical guide rather than an absolute threshold. The calculator provides a numerical value, but the meaning of that value depends on the patient’s overall context, the rest of the chemistry panel, and whether the reported carbon dioxide reflects true bicarbonate status.
How to Interpret a High or Low Anion Gap
A high anion gap often points to the presence of extra acids in the blood. This is a typical clue in metabolic acid buildup, where acid accumulation or reduced acid clearance shifts the balance between measured cations and anions. In everyday terms, a high value can signal a more serious underlying issue that needs additional workup.
A normal anion gap does not always rule out an acid-base problem. Some forms of acidosis can occur with a gap that remains within the expected usual range. For that reason, the anion gap should be interpreted together with pH, bicarbonate, chloride, and other findings rather than used alone.
A reduced anion gap is less common, but it can be clinically meaningful. One major reason is a low level of serum albumin, because albumin contributes negatively charged proteins that affect the balance of measured ions. When albumin is reduced, the observed gap may appear lower even if other processes are present.
Interpreting a gap also depends on whether the patient has a mixed disorder. For example, a person may have metabolic acidosis with a gap that seems only mildly elevated if another process is lowering the bicarbonate or if the electrolyte pattern is altered by treatment or fluid shifts. This is where careful assessment matters more than the number alone.
Typical Causes of Abnormal Readings
Several conditions can cause a raised anion gap. A classic cause is lactic acidosis, where lactate builds up due to reduced oxygen delivery, shock, severe illness, or other metabolic stress. Another frequent cause is ketoacidosis, which occurs when ketone bodies accumulate in diabetes, starvation, or other states of impaired carbohydrate use.
Kidney failure can also elevate the gap because the kidneys are less able to clear acid load and other unmeasured anions. As kidney function worsens, acids build up and the measured electrolyte pattern may alter. In this situation, the anion gap becomes one part of a broader evaluation of metabolic waste retention and acid handling.
Toxin ingestion is another important category. Certain ingestions can create a high gap by introducing acids or toxic metabolites into the blood. In the right clinical scenario, the anion gap may provide an early clue that prompts urgent investigation. The calculation itself does not identify the toxin, but it can support timely recognition of an abnormal pattern.
On the other hand, a reduced anion gap may be associated with low albumin, laboratory artifact, or uncommon changes in serum proteins and ions. While less frequent than high values, a low result should not be ignored if it is unexpected or inconsistent with the patient’s condition. It may require repeat testing or broader evaluation of the chemistry panel.
Adjusting the Anion Gap for Albumin
Correction for albumin is an key part when interpreting the anion gap, especially in patients with hypoalbuminemia. Because albumin is a main unmeasured anion, a low albumin level can make the anion gap look falsely normal or low. In these cases, the unadjusted result may downplay the true acid burden.
An corrected anion gap corrects for this effect by adjusting the calculated value based on the albumin concentration. The exact adjustment method can vary, but the purpose is the same: to enhance accuracy in interpretation when albumin is below normal. This is particularly valuable when assessing suspected metabolic acidosis in admitted or chronically ill patients.
The need for correction becomes clearer when the laboratory pattern seems inconsistent with the clinical picture. For example, a patient may have signs of acid-base disturbance, but the uncorrected gap is not elevated. In that setting, checking albumin and applying correction can help reveal an abnormality that would otherwise be hidden.
Albumin correction does not substitute for the original calculation. Instead, it adds another layer of information to the same equation-based assessment. The adjusted number should still be interpreted with the clinical picture, especially if there are mixed disorders, fluid changes, or multiple abnormal laboratory values.
Drawbacks of an Anion Gap Calculator
Though an Anion Gap Calculator is useful, it has a number of restrictions. One major is lab variation. Multiple analyzers and methods can yield mildly different sodium, chloride, or carbon dioxide values, which changes the final result. This means the same patient could have a mildly varied number depending on where the sample is processed.
Measurement error can also impact the outcome. Tiny inaccuracies in any one of the input values can change the final calculation. Since the anion gap is derived from a subtraction-based formula, minor differences in chloride or CO2 may have a meaningful effect on the result, especially if the gap is near the edge of the reference range.
Another limitation is that the calculator reflects only part of the acid-base picture. It does not directly measure blood pH, lactate, ketones, renal function, or toxic substances. For that reason, the number should be treated as one part of wider blood test interpretation, not as a stand-alone answer.
The best use of the tool is as a quick screening aid. It can identify a possible abnormality and direct further evaluation, but it cannot determine the cause on its own. The same numerical value can have different meaning depending on the patient’s symptoms, medications, hydration status, and underlying illness. Effective medical decision-making always combines the calculation with the rest of the clinical picture.
FAQs
How do you calculate the anion gap using sodium, chloride, and CO2?
Apply the formula sodium − (chloride + CO2). In this calculator workflow, carbon dioxide is used as a convenient substitute for bicarbonate. The result is the anion gap, usually reported in mEq/L.
What is the normal range for an anion gap?
The normal anion gap depends on the laboratory and method used. That is why you should always compare the result to the report’s reference range. Different serum chemistry analyzers can generate slightly different expected values.
What does a elevated anion gap mean?
A high anion gap typically points to metabolic acidosis due to extra unmeasured acids in the blood. Frequent causes include lactic acidosis, ketoacidosis, renal failure, and some types of toxin ingestion.
Why might the anion gap be low?
A reduced anion gap is often related to low albumin, especially in hypoalbuminemia. It can also be caused by lab-related issues or less common changes in serum proteins and electrolytes. When the result is unexpected, repeat testing and broader evaluation may be appropriate.
Should albumin be considered when interpreting the anion gap?
Absolutely. Albumin correction is important because albumin is a major unmeasured anion. When albumin is low, the measured gap may underestimate the true abnormality. An adjusted anion gap can improve interpretation and make the result more useful for assessing acid-base balance.