How the Anion Gap Measures
The anion gap is a calculated value that helps clinicians understand electrolytes and broader acid-base balance. It is not directly measured on a blood test; instead, it is calculated from common lab values, notably sodium, chloride, and bicarbonate. Because these numbers are part of the same chemistry panel, changes in one can influence the final result and its clinical significance.
At a basic level, the anion gap estimates the difference between the main positively charged and negatively charged ions in the blood. This makes it a useful diagnostic clue when assessing an unexpected result on a blood test. It can help show whether a patient may have a hidden acid-base problem, such as metabolic acidosis, or whether the issue is better explained by a change in serum levels of proteins or a possible measurement error.
Most often, clinicians consider sodium, chloride, and bicarbonate together on the basic metabolic panel. These values are the backbone of many routine lab reviews. If sodium is low, the anion gap can look different even when the underlying chemistry has not changed much. That is why understanding the formula matters before drawing conclusions about the normal range or deciding whether an abnormal value is meaningful.
How an Anion Gap Calculator Functions
An Anion Gap Calculator is a useful tool that does the same analysis clinicians use when assessing lab values. It uses the available serum bicarbonate, sodium, and chloride values to estimate the gap. Some calculators also ask for albumin or serum albumin because low protein levels can cause the result appear falsely low and may require albumin correction.
The calculator is useful because it turns raw lab values into an interpretation guide. Rather than looking at sodium or chloride alone, it assists show how the numbers fit together. This enhances result accuracy when evaluating an unexpected result and gives a more complete picture of the patient’s electrolyte balance.
In practical use, the calculator supports clinicians in distinguishing whether the pattern suggests a high anion gap or a low anion gap. A high value may suggest excess unmeasured acids, while a low value may point to low albumin, a lab artifact, or less common causes such as paraproteins. The calculator does not replace judgment, but it helps with faster, more structured lab interpretation.
Because the anion gap is calculated from routine chemistry data, even small shifts in sodium, chloride, or bicarbonate can change the outcome. That is why the calculator should always be used with the rest of the panel and the patient’s overall picture, not in isolation.
Can Reduced Sodium Change the Anion Gap?
Indeed, hyponatremia can impact the anion gap, but the relationship is rarely simple. Since sodium is included of the formula, a decreased sodium value can alter the calculated result. However, a low sodium level does not automatically mean the anion gap is truly abnormal. The result may reflect the formula itself, the underlying cause of the sodium change, or a measurement error.
From a chemistry standpoint, the body maintains electroneutrality, meaning total positive and negative charges stay balanced. The anion gap is a way of measuring the portion of that balance not directly captured by the measured ions. If sodium falls, the calculation can shift, but whether that shift matters depends on the full lab pattern and clinical context.
As an example, if sodium is low because of fluid imbalance or a dilutional state, the gap may appear lower without a true change in acid-base status. If chloride or bicarbonate also changes, the effect may be more obvious. This is why clinicians should not interpret sodium in isolation. They use the entire panel to decide whether the result reflects a real disorder or a misleading number.
Low sodium can also coexist with conditions that cause a truly abnormal anion gap. In that setting, the sodium change is not the primary driver of the gap, but it may complicate the lab interpretation. The question is not simply whether sodium is low, but whether the low sodium is changing the calculation enough to obscure the underlying cause.
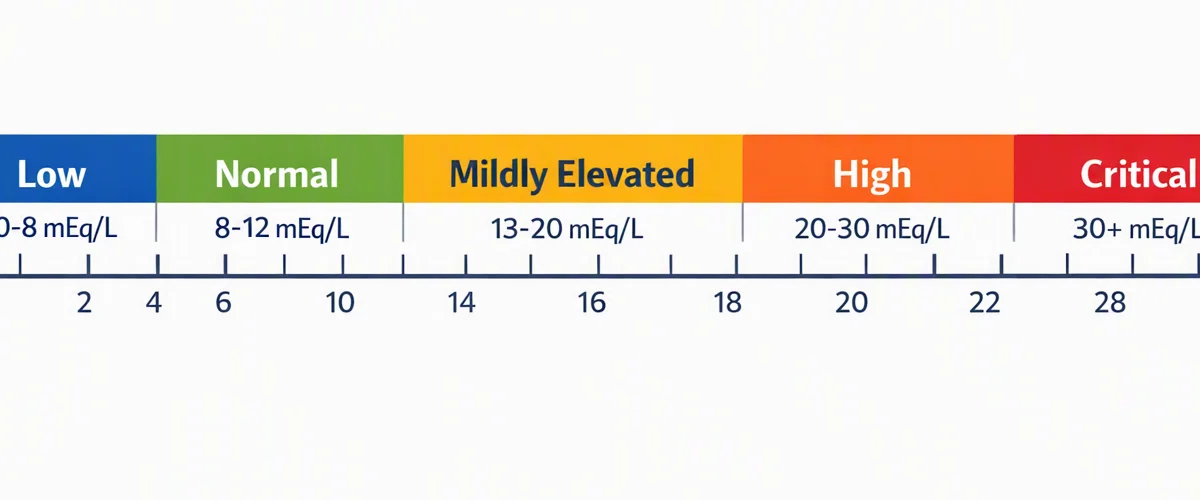
Common Reasons for Hyponatremia and an Altered Anion Gap
Hyponatremia and an altered anion gap often occur together because the same illness can influence fluid balance, kidney handling of electrolytes, and acid formation. One frequent reason is dehydration. Even though dehydration is often associated with concentrated labs, severe fluid loss can alter sodium and other values in ways that make interpretation tricky, especially if bicarbonate also changes.
Kidney disease is another important cause. As the kidneys cannot remove acids efficiently, the body may develop metabolic acidosis. In that setting, the anion gap anion gap in chronic kidney disease may rise because unmeasured acids build up. Kidney dysfunction can also affect sodium regulation, making the lab pattern more complex.
SIADH, or syndrome of inappropriate antidiuretic hormone secretion, is a well-known cause of hyponatremia. In SIADH, water retention dilutes sodium, and the anion gap may look different depending on the rest of the chemistry panel. The anion gap itself may not be the main issue, but it can still help detect whether another acid-base disorder is present.
Some patients with low sodium and abnormal acid-base findings have a mixed problem. For example:
- Low sodium with low bicarbonate may suggest a metabolic process that needs closer review. Low sodium with elevated chloride may lower the anion gap or point away from a high-gap disorder. Kidney disease can contribute to both sodium imbalance and metabolic acidosis.
The key point is that low sodium may be a clue, not the diagnosis itself. A thorough review of electrolytes, serum bicarbonate, and other lab values is needed to determine the real diagnostic clue behind the pattern.
Decreased Anion Gap vs Elevated Anion Gap
A low anion gap and a increased anion gap suggest distinct causes. A high anion gap usually points toward too much acids in the blood, while a low anion gap often reflects decreased albumin, a lab issue, or rare disorders. That difference matters because the treatment approach depends on the direction of the change.
Albumin is one of the main reasons a low anion gap can occur. Because albumin carries a negative charge, low albumin can reduce the gap even when sodium, chloride, and bicarbonate are otherwise stable. This is why albumin correction is often necessary. A corrected anion gap may indicate that the result is less abnormal than it first appeared.
By contrast, a high anion gap often appears in conditions such as lactic acidosis and ketoacidosis. In lactic acidosis, the body builds up lactate due to poor oxygen delivery or impaired metabolism. In ketoacidosis, ketones accumulate when the body uses fat for fuel. Both conditions can produce a high anion gap metabolic pattern that requires prompt attention.
Paraproteinemia can also lead to a low anion gap. Abnormal proteins in the blood may alter the charge balance enough to affect the calculation. This is less common than low albumin, but it is clinically important when the result does not fit the rest of the labs.
Thinking in terms of low versus high anion gap helps focus the differential. It also keeps the clinician focused on the reference range, the surrounding chemistry, and the true clinical significance of the result rather than the number alone.
If a Lower Anion Gap Is a Lab Artifact
Not all low anion gap indicates a medical problem. At times the result is a laboratory error or other testing artifact. This is why result review should cover the possibility of a specimen issue, especially when the number does not match the patient’s symptoms or other findings.
One especially important artifacts is pseudohyponatremia. In this case, the measured sodium may look reduced than it actually is because of unusual sample composition, such as very high protein or lipid levels. If sodium is falsely low, the calculated anion gap may also appear misleading. That may lead to a unclear pattern interpret anion gap unless the sample is repeated or checked with a different method.
A different frequent step is testing again. In case the finding is surprising, repeating the blood test helps determine whether the issue is genuine or due to natural fluctuation, collection problems, or instrument-related problems. It is especially vital when the lab pattern is inconsistent with the patient’s condition.
Whenever sodium, chloride, or bicarbonate do not fit the clinical picture, first ask whether the value is repeatable before concluding a genuine acid-base problem.
A reduced anion gap resulting from artifact is frequently corrected when the sample is checked again. That is why clinicians closely watch measurement error and how the specimen was drawn, handled, and evaluated.
Ways Providers Interpret the Result
Providers rarely interpret the anion gap by itself. They review the basic metabolic panel at first, then add an arterial blood gas as needed to clarify the acid-base status in greater detail. These tests together give a clearer view of the patient’s chemistry and respiratory condition.
Assessment often begins with checking sodium, chloride, bicarbonate, and serum albumin. If albumin is low, the anion gap may need albumin correction before it can be interpreted properly. This is critical because a corrected anion gap may change the clinical picture from abnormal to almost normal.
The next stage is putting the result into clinical context. Is the patient sick, dehydrated, confused, short of breath, or demonstrating kidney dysfunction? Are there symptoms that suggest lactic acidosis or ketoacidosis? Does the pattern fit SIADH, or is there evidence of paraproteinemia? These considerations help determine whether the number represents a true disorder or a transient lab finding.
Clinicians also compare the result with prior labs when available. A sudden change may be more concerning than a mildly abnormal value that has remained stable. This method helps identify the underlying cause and supports better decision-making around further testing, treatment, or observation.
In short, the anion gap is a calculated value, but its interpretation is a clinical process. The best interpretation guide pairs the calculator result with the patient’s symptoms, lab trend, and possible diagnosis.
When to Seek Medical Evaluation
Low sodium alongside an abnormal anion gap warrants medical evaluation when they are associated with worrisome symptoms or when the result is severe. In some cases, mild changes can be watched, but significant abnormalities can indicate a serious disorder that should be addressed quickly.
Extra caution is needed for severe hyponatremia. If sodium is very low, the brain can be affected, leading to confusion, headache, nausea, weakness, or more serious neurologic symptoms. These findings should not be ignored, especially if the patient also has an abnormal anion gap or signs of metabolic illness.
Seek urgent emergency care if abnormal labs occur along with fainting, seizures, severe confusion, trouble breathing, chest pain, or marked decline in alertness. These may suggest a life-threatening electrolyte or acid-base disturbance.
A low anion gap without symptoms may still need follow-up, especially if the result is persistent or paired with low albumin, kidney disease, or suspected paraproteinemia. Even when the issue turns out to be a lab artifact, confirmation matters because it prevents missed diagnoses and avoids unnecessary treatment.
The most prudent approach is to treat the Anion Gap Calculator as a guide, not a diagnosis on its own. If the result is unexpected, repeat the labs, review the basic metabolic panel, and discuss the findings with a clinician who can interpret them in context.
FAQ
Can low sodium lower the anion gap?
Yes, it can. Because sodium contributes to the anion gap equation, low sodium can lower the calculated value. However, the result may also reflect the underlying condition causing the sodium change or a lab artifact, so it should be interpreted with chloride, bicarbonate, and serum albumin.
Can hyponatremia lead to a low anion gap?
A low sodium level can contribute to a low anion gap, but it does not always cause one by itself. The bigger question is why the sodium is low and whether other values, such as chloride and bicarbonate, support a true acid-base disorder.
What is the leading cause of a low anion gap?
Hypoalbuminemia is one of the primary causes of a low anion gap. For this reason albumin correction is crucial. Next, lab artifact and measurement issues are also frequent explanations, especially when the result does not align with the clinical picture.
Can a low anion gap be due to a lab error?
Yes. A low anion gap can result from a laboratory error, specimen concern, or pseudohyponatremia. Repeat testing is often the best first step when the value is unusual or not aligned with other lab findings.
When should I worry about abnormal sodium and anion gap results?
You should get medical evaluation if abnormal sodium and anion gap results occur with symptoms such as mental confusion, severe weakness, vomiting, shortness of breath, or signs of severe hyponatremia. Emergency care is necessary if there are neurologic symptoms or a quickly deteriorating condition.