What Is the Anion Gap?
The anion gap is a computed value used to assist evaluate acid-base balance and electrolyte irregularity. It comes from routine blood chemistry and measures the main reported cations and anions in the blood, especially sodium and chloride, along with serum bicarbonate. Because not every charged particle is directly measured, the anion gap helps identify the occurrence of unmeasured anions and provides a helpful diagnostic clue in metabolic acidosis.
In practical terms, the anion gap shows the difference between measured electrolytes in a serum chemistry panel. A typical anion gap formula anion gap in chronic kidney disease uses sodium, chloride, and bicarbonate to estimate whether there are extra acids in the blood or whether bicarbonate has been lost. Clinicians use this result as part of the larger interpretation of a laboratory result, not as a standalone answer.
The value is most helpful when viewed in clinical context. A normal or elevated number does not by itself tell the whole story about severity, because the body may be in an acidotic state for different reasons. That is why the anion gap is often paired with other tests, including arterial blood gas testing, to understand the full metabolic disturbance.
How an Anion Gap Calculator Works
An anion gap calculator simplifies the calculation from blood values, usually sodium, chloride, and serum bicarbonate. This helps you quickly estimate whether the gap is within the expected reference range or whether it suggests high anion gap acidosis. The calculator is especially useful when reviewing multiple lab results or tracking changes over time.
Many modern calculators also include albumin correction. Albumin is a negatively charged protein, so lower albumin can make the measured gap appear deceptively normal. An albumin-corrected anion gap modifies the result to better reflect true acid burden. This corrected gap can reveal hidden acid retention even when the uncorrected number seems unremarkable.
Because albumin changes the expected baseline, a normal value on the uncorrected calculation may not truly be normal. In other words, the corrected gap is often more informative than the raw number, especially when the blood chemistry suggests an acidotic state but the anion gap appears borderline. A good calculator supports better interpretation by accounting for these physiologic shifts.
Using an anion gap calculator does not replace judgment. It is a calculated value that must be considered alongside pH, base excess, serum electrolytes, and the overall pattern of the metabolic disturbance. The calculator is a tool, but the diagnosis comes from combining the numbers with the patient’s condition.
Can Marked Acidosis Have a Typical Anion Gap?
Indeed. Severe acidosis can definitely occur with a typical anion gap. That is the key point many people miss. A normal gap does not exclude significant metabolic acidosis; it only indicates that the acid-base problem is not being driven by a large accumulation of unmeasured anions. In normal anion gap acidosis, the main problem is usually depletion of bicarbonate or a related shift in chloride.
This pattern is also called hyperchloremic acidosis because chloride increases to maintain electrical neutrality as bicarbonate declines. The result is significant acidemia in some cases, yet the anion gap stays within the expected range. The body is still acidic, but the chemistry pattern is not the same from high anion gap acidosis.
In severe cases, the serum bicarbonate may be very low, and the pH can be markedly reduced. The anion gap remains normal because the fall in bicarbonate is balanced by a rise in chloride. This is why a normal gap should never be interpreted as “no acidosis.” It simply points the clinician toward bicarbonate loss or chloride retention rather than excess unmeasured acids.
Knowing this distinction is important in differential diagnosis. A patient with a normal anion gap and low bicarbonate may still be quite ill. The severity of the acidotic state is reflected more directly by pH and base deficit than by the gap itself.
Frequent Causes of Normal Gap Metabolic Acidosis
Several conditions can cause normal anion gap acidosis. A very common cause is diarrhea, which results in direct bicarbonate loss from the gastrointestinal tract. When bicarbonate is depleted, chloride often increases to preserve electroneutrality, creating a normal gap pattern.
Renal tubular acidosis is another major cause. In these disorders, the kidneys fail to appropriately manage hydrogen ions or bicarbonate, causing persistent metabolic acidosis. Depending on the subtype, the blood may show low serum bicarbonate with normal or increased chloride. Even so, the anion gap can remain normal even when the acidosis is clinically significant.
Other common mechanisms involve either inadequate bicarbonate regeneration or excessive chloride exposure. Large-volume saline administration, for example, can contribute to chloride retention and a hyperchloremic pattern. This is not always dramatic on the surface, but it can substantially affect acid-base balance and blood chemistry.
These conditions share a similar laboratory signature:
- Reduced serum bicarbonate Relatively high chloride Unremarkable or near-normal anion gap Evidence of metabolic acidosis on blood gas testing
The pattern supports a targeted diagnostic approach. Instead of searching first for lactate or ketoacidosis, clinicians should consider bicarbonate loss, chloride retention, and kidney-related causes when the gap is normal.
When a Normal Anion Gap Can Be Misinterpreted
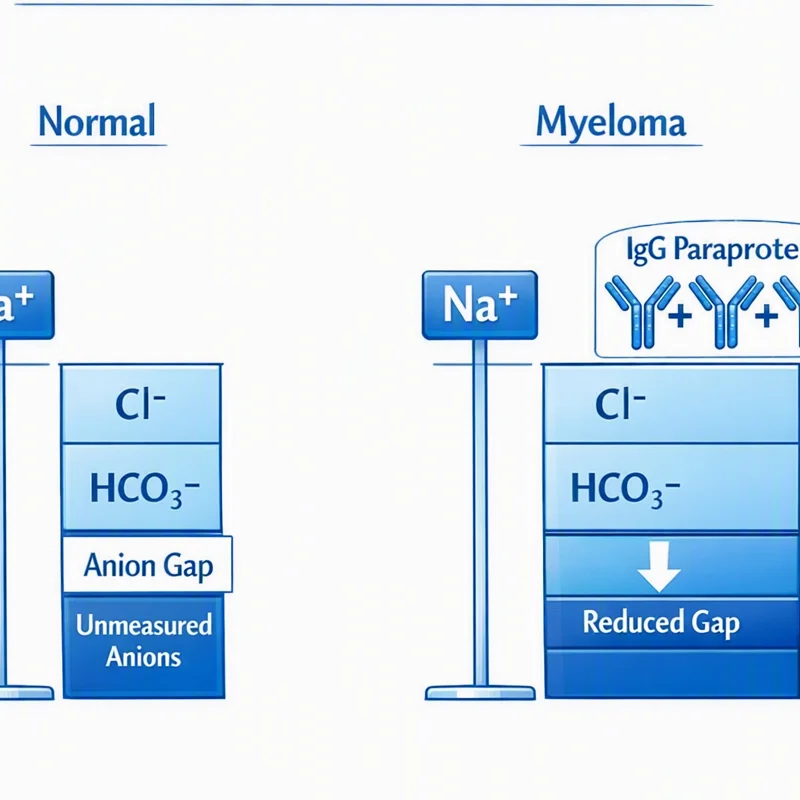
A regular anion gap can be misread when other factors mask the actual acid burden. One important issue is albumin. Because albumin is a key unmeasured anion, decreased albumin can lower the measured gap. Without albumin correction, a patient with severe acidemia may seem to have a comforting value even though the corrected gap is actually high.
This get more info matters particularly in a mixed acid-base disorder. As an example, a patient may have both lactic acidosis and bicarbonate loss, or ketoacidosis plus concurrent hyperchloremic acidosis. One process may raise the gap while another pushes it back toward normal. In that setting, the measured result can mask the presence of high anion gap acidosis.
Lactate and ketoacidosis are classic causes of elevated gaps, but they may not always present in a clean, isolated pattern. If the body has already lost bicarbonate or received large amounts of chloride-containing fluid, the gap may seem normal despite a serious metabolic problem. That is why the calculated number must be viewed with the full clinical picture.
In short, a normal gap can represent:
- Genuine normal anion gap acidosis A blended disorder that offsets the numbers Hypoalbuminemia masking an elevated corrected gap A timing issue, where lab values shift as the condition evolves
So the normal result is not the final step of the workup. It is a diagnostic clue that should be weighed against the patient’s symptoms, serum electrolytes, and other studies.
How to Read Values in Clinical Context
Assessing the anion gap properly requires integrating several clinical clues. The arterial blood gas supplies key information about pH and ventilation, while the serum chemistry panel shows the underlying electrolyte pattern. Taken together, they indicate whether the patient has acidemia, its severity, and whether compensation is present.
The pH tells you whether the blood is acidotic or alkalemic. The base excess helps measure the degree of metabolic abnormality, while serum bicarbonate indicates the buffering status directly. If pH is low and bicarbonate is low, the patient is definitely in a metabolic acidosis, even if the anion gap is normal.
Clinical context matters because the same laboratory result can mean different interpretations depending on the situation. A normal gap in a patient with diarrhea may fit bicarbonate loss. In someone with diabetic symptoms, the same result may suggest a mixed acid-base disorder or a corrected gap that should be reviewed carefully. The interpretation is never just arithmetic; it is clinical reasoning.
Practical points to consider include:
- Assess the albumin level and evaluate the corrected gap Examine the serum chemistry panel for chloride and bicarbonate trends Corroborate the acid-base status with arterial blood gas results Assess for evidence of compensation or a mixed disorder Rely on pH and base excess to assess severity, not only the anion gap
The best approach is to treat the anion gap as one part of a broader evaluation. It aids in the differential diagnosis, but it does not replace a full acid-base assessment.
FAQ
Can severe acidosis happen with a normal anion gap?
Indeed, it can. Severe acidosis can occur with a normal anion gap, especially in normal anion gap acidosis. This usually happens as bicarbonate is depleted or chloride rises to balance the decrease in bicarbonate. The patient may still be markedly acidotic even when the gap falls within the normal range.
What conditions cause a normal anion gap metabolic acidosis?
Common causes include diarrhea, renal tubular acidosis, and other sources of bicarbonate loss. Chloride retention may also create this pattern. These conditions typically create hyperchloremic acidosis with a normal or near-normal anion gap.
Why does albumin matter when interpreting the anion gap?
Because albumin is a major unmeasured anion, low albumin can cause the anion gap to seem falsely normal. Albumin correction helps reveal the true corrected gap. This matters most when the clinical presentation suggests more severe metabolic acidosis than the initial number indicates.
Is a normal anion gap possible in ketoacidosis or lactic acidosis?
Indeed, they can. Although ketoacidosis and elevated lactate usually cause high anion gap acidosis, the gap may appear normal in a mixed acid-base disorder or if hypoalbuminemia is present. Prior bicarbonate loss or chloride loading can also mask the expected elevation.
How is an anion gap calculator used alongside blood gas results?
An anion gap calculator should be used in combination with arterial blood gas results, not in place of them. The calculator helps determine whether the pattern matches normal or high anion gap acidosis, while the blood gas displays pH, base excess, and overall severity. Used together, they give a more complete interpretation of the acid-base disturbance.