What Is the Anion Gap?
The anion gap is a derived number that helps doctors evaluate the equilibrium of charged particles in the blood. It is based on common electrolytes obtained on a chemistry panel, especially sodium, chloride, and bicarbonate. Because not all ions are directly measured, the anion gap reflects the amount of unmeasured anions in the bloodstream.
A simple anion gap formula is often used in blood chemistry:
Anion gap = sodium − (chloride + bicarbonate)
This result is valuable because it gives clues about acid-base balance and can help recognize an acid-base disorder, especially metabolic acidosis. When the gap is higher than expected, it may indicate acid retention or an increase in unmeasured acids. When it is lower than expected, it may be due to albumin changes, laboratory issues, or other causes.
Although the anion gap is only one piece of laboratory interpretation, it has important clinical significance. It is commonly used alongside the rest of the serum electrolytes, the patient’s symptoms, and sometimes blood gas analysis to help direct a diagnostic evaluation.
How an Anion Gap Calculator Works
An Anion Gap Calculator performs the calculation so the output can be reviewed quickly during medical evaluation. You input the lab values for sodium, chloride, and bicarbonate, and the calculator returns the anion gap. Some versions also offer albumin correction, which can be especially helpful when serum albumin is low.
Because albumin is a major anionic protein in blood, changes in albumin can affect the measured gap. A calculator that includes corrected anion gap logic can improve interpretation, especially in pregnancy or other settings where blood protein levels shift. This is part of better laboratory interpretation and helps differentiate a true metabolic disturbance from a value that looks abnormal because of protein changes.
In practice, the calculator does not take the place of clinical judgment. It is a tool to guide evaluation of acid-base balance, detect possible electrolyte imbalance, and recognize when the pattern suggests hidden acids or acid retention. If the result is unusual, clinicians usually review the broader pattern in the lab work rather than the number alone.
For example, a calculator may be valuable when someone has nausea, dehydration, or suspected ketoacidosis. It can rapidly show whether the blood chemistry points toward a high-gap process or whether a low result is more likely related to albumin or other factors.
Does Pregnancy Alter the Anion Gap?
The short answer is: pregnancy can alter the anion gap, but often only mildly. The effect is usually indirect and linked to pregnancy physiology rather than a disease condition. During normal pregnancy, several physiologic changes occur that can alter the usual laboratory pattern.
One major change is expansion of plasma volume, which spreads out some blood components. Pregnancy also causes respiratory alkalosis because breathing tends to become slightly more rapid and deeper than usual. This lowers carbon dioxide levels and can lead to adaptive changes in bicarbonate handling.
At the same time, the kidneys and other organs undergo renal adaptation to maintain maternal and fetal health. These adaptations influence electrolytes, protein concentrations, and acid-base status. As a result, the anion gap in pregnancy may not appear the same as it does outside of pregnancy.
That said, pregnancy does not automatically cause a dangerous anion gap abnormality. A mildly different value may still be normal for that physiologic state. The key is to interpret the result together with symptoms, the full electrolyte profile, and whether there is any evidence of metabolic acidosis or another acid-base issue.
The reason the Anion Gap May Look Different in Pregnancy
Various pregnancy-related factors can lead the anion gap look lower or in other ways different from a pre-pregnancy baseline. The key factor is a change in albumin. Since albumin contributes to the pool of unmeasured anions, a lower albumin level can lower the measured gap even when acid-base status is still stable.
This reduction is often described as dilutional hypoalbuminemia. In pregnancy, expanding plasma volume can thin out albumin concentration, which lowers the apparent anion gap. In addition, increased renal blood flow and other aspects of renal adaptation may influence how the body handles electrolytes and bicarbonate.
There is also a typical tendency toward mild respiratory alkalosis, which can lead the kidneys to excrete more bicarbonate over time. That compensatory process can slightly change blood chemistry, especially if the person is dehydrated, vomiting, or not eating well. These compensatory changes can make the gap look different even without a major disorder.
In other words, pregnancy may shift the baseline because of changes in protein concentration, ventilation, and kidney function. This is why an isolated abnormal number should be interpreted cautiously and in light of the full picture.
What Counts as a Usual Anion Gap in Pregnancy?
There is no single fixed reference range that applies to every pregnant patient and each laboratory. Various labs use different methods, and those methods change the reported values. In addition, laboratory values may vary depending on whether potassium is included in the calculation and whether the lab’s method has been standardized to a particular analyzer.
In pregnancy, a result that is slightly lower than usual may still fit the expected pattern if albumin is reduced and the rest of the clinical picture is stable. That is why albumin correction is often important. A low measured value may normalize after correction, revealing a functional normal anion gap.
The best way to interpret the number is to compare it with the lab’s own reference range, then ask whether pregnancy-related changes explain the finding. If there is no sign of illness and the patient has stable electrolytes, the result may simply reflect normal pregnancy physiology. If symptoms or other abnormalities are present, the interpretation changes.
Because of these factors, the most useful approach is not to chase a single number, but to ask whether the lab pattern suggests a real https://anion-gap-analyzer282.urbanvellum.com/posts/how-to-use-an-anion-gap-calculator-step-by-step acid-base disorder. That often means reviewing the bicarbonate, albumin, and other electrolytes together.
Raised Anion Gap Factors to Be Aware Of During Pregnancy
A raised anion gap usually means there are additional acids in the blood. During pregnancy, various causes deserve special attention because they may affect both mother's and fetal safety. The main include ketoacidosis, diabetic ketoacidosis, and lactic acidosis.
Diabetic ketoacidosis can occur in pregnancy and may develop at lower glucose levels than expected. This makes it simple to miss if clinicians focus only on blood sugar. In this condition, fat breakdown leads to ketone buildup, which increases the gap and causes metabolic acidosis.
Ketoacidosis can also happen with prolonged vomiting, poor oral intake, or severe dehydration. Pregnancy increases vulnerability because energy needs are higher and fasting tolerance is lower. If ketones are present in urine or blood, the finding should be taken seriously.
Lactic acidosis is another possible cause of a high gap. It may result from infection, hypoperfusion, severe dehydration, or other stressors that reduce oxygen delivery or increase lactate production. In these cases, lactate is a valuable clue during diagnostic workup.
Less common but important causes include toxins such as certain medications or exposures that generate unmeasured acids. A high gap always requires a broader review of symptoms, medication history, and blood gas results. When pregnancy is involved, prompt evaluation matters because the underlying metabolic disturbance can worsen quickly.
Reduced Anion Gap Factors and Cautions
A reduced anion gap is not as common than a high one, but it can still be meaningful. The main explanation is hypoalbuminemia, especially when pregnancy has caused hemodilution of plasma proteins. Since albumin is a major unmeasured anion, lower albumin generally means a lower measured gap.
One other explanation is lab error. Because the anion gap is calculated from several measurements, a problem in any one result can distort the final number. A repeat test is often advisable if the value does not match the clinical picture.
Additional causes include paraproteinemia, where abnormal proteins affect the charge balance, though this is less typical in pregnancy. Hyperchloremia can also lower the gap by raising chloride relative to sodium and bicarbonate. This pattern may be seen with various fluid shifts or after treatment with chloride-rich fluids.
When a low value appears, it is important to ask whether the finding is genuine or whether it is explained by dilutional hypoalbuminemia and pregnancy-related changes. A corrected calculation often makes clear the situation. If the value remains unexpectedly low, the clinician may evaluate for other metabolic or protein-related conditions.
How to Read an Anion Gap Alongside Other Labs
The anion gap should by no means be interpreted by itself. A close review of the electrolyte panel, acid-base balance, and clinical situation gives a more complete picture. If there is concern for metabolic acidosis, an arterial blood gas or other blood gas study can reveal the pH, bicarbonate, and respiratory compensation.
Measuring lactate is useful when there is concern for tissue hypoperfusion, infection, or another cause of lactic acidosis. If the person has poor intake, diabetes, or vomiting, ketones should also be measured because they can detect ketoacidosis or other forms of acid buildup.
In pregnancy, the pattern of the other electrolytes is important as much as the gap itself. For example, a low bicarbonate with a high gap suggests a true acid burden. A low gap with low albumin may not indicate a dangerous process. The same number can suggest different things depending on the rest of the lab picture.
This is why blood gas analysis, serum electrolytes, and clinical symptoms should all be considered together. A thoughtful review helps reduce the risk of missing a serious acid-base disorder and improves diagnostic accuracy.
When to Get Medical Review
Pregnancy can make interpretation more nuanced, but some symptoms should lead to medical review regardless of the exact anion gap number. These include shortness of breath, persistent vomiting, confusion, or signs of dehydration. If these symptoms occur with abnormal lab results, the situation may indicate a significant metabolic issue.
Checking for ketones is especially important if there is poor intake, vomiting, diabetes, or concern for ketoacidosis. Pregnancy can lower the threshold for ketone formation, so symptoms plus ketones need prompt attention. A high gap in this setting may indicate an emergency.
Seek prompt review if there is progressive exhaustion, breathing quickly, abdominal pain, or a test pattern suggesting metabolic acidosis. Any combination of symptoms and abnormal blood test results needs swift evaluation, particularly because pregnancy involves both the mother’s health and fetal well-being.
If an Anion Gap Calculator shows a result outside the normal reference range, that alone does not confirm risk. But if it aligns with symptoms or other abnormal values, it should not be dismissed.
Frequently Asked Questions
Does pregnancy lower or raise the anion gap?
Pregnancy can somewhat lower the anion gap in some people, mainly because of plasma volume expansion and dilutional hypoalbuminemia. Slight variations are often due to normal pregnancy physiology rather than disease. A higher value is more concerning when it reflects a true acid buildup such as metabolic acidosis.
Is an anion gap of 8 normal in pregnancy?
It may be. Whether an anion gap of 8 is normal depends on the lab’s reference range, the measurement method, and the person’s albumin level. In pregnancy, a slightly lower number may still be acceptable if the rest of the electrolytes and clinical findings are comforting.
Should the anion gap be corrected for albumin during pregnancy?
Yes, albumin correction is often useful during pregnancy because albumin commonly falls with plasma volume expansion. A corrected anion gap can provide a better estimate of true acid-base status than the uncorrected number alone.
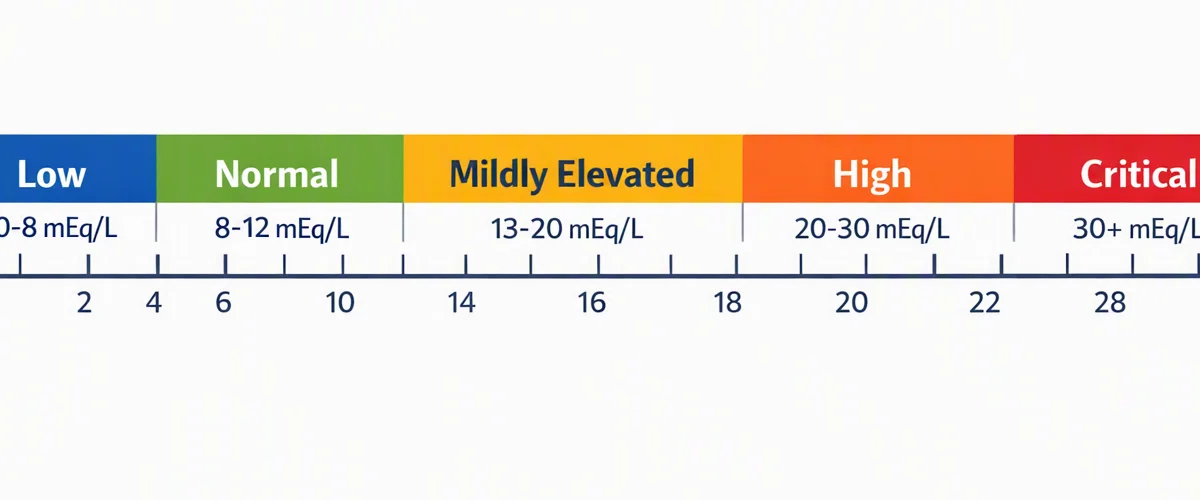
What causes a high anion gap in pregnancy?
Common causes include diabetic ketoacidosis, other forms of ketoacidosis, and lactic acidosis. Less commonly, toxins or other metabolic problems can raise the gap. These conditions may lead to metabolic acidosis and need prompt evaluation.
When should a expecting person with an abnormal anion gap obtain medical care?
Obtain medical care right away if an abnormal anion gap occurs with shortness of breath, vomiting, confusion, or positive ketones. This combination can suggest a significant acid-base imbalance, and pregnancy heightens the need for careful diagnostic evaluation.