An anion gap calculator is a practical diagnostic tool for estimating the distance between measured positive ions and measured negative ions in a serum chemistry or metabolic panel. Providers use the anion gap to support clinical interpretation of an acid-base disorder, especially when evaluating metabolic acidosis and other forms of electrolyte imbalance. By combining the values for sodium, potassium, chloride, and bicarbonate, you can infer how many unmeasured anions may be present in the blood.
This article explains the calculation step by step, how to read a lab result, and why the corrected anion gap matters when serum albumin is low. It also explores common causes of a high anion gap and a low anion gap, plus pitfalls such as measurement error and laboratory error.
What the Anion Gap Assesses
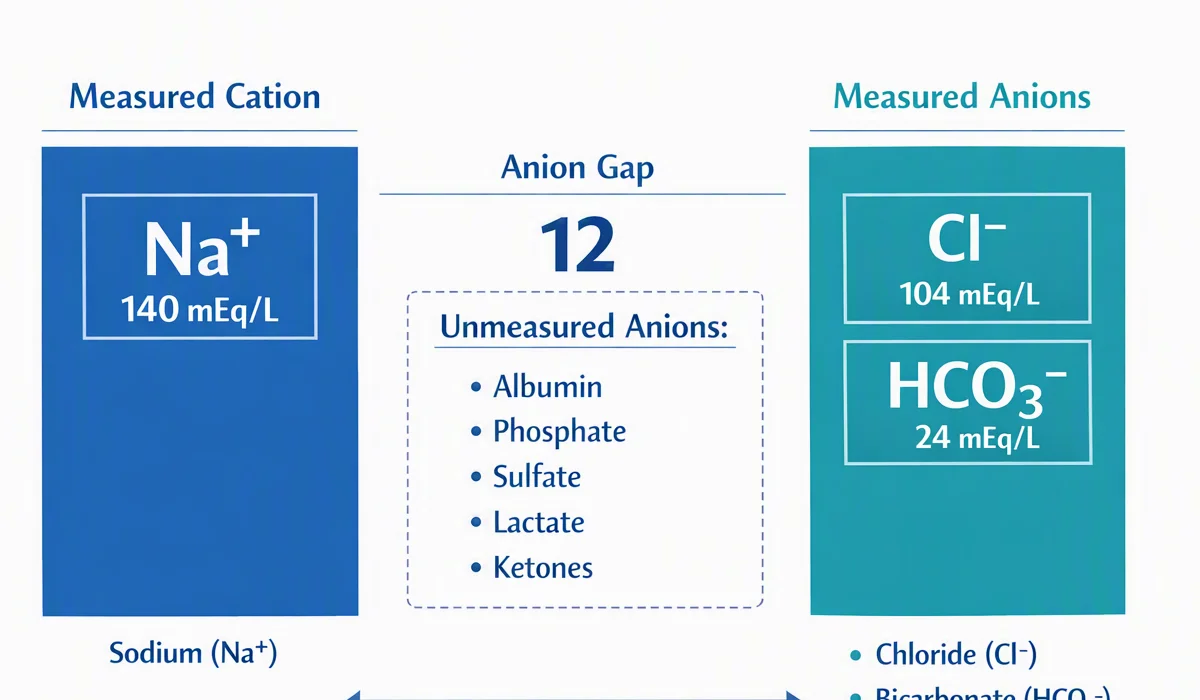
The anion gap is an approximation of the gap between the positive and negative particles measured on common electrolytes. Since standard testing does not measure every ion in blood, the gap reflects the presence of unmeasured ions or unmeasured anions that support acid-base balance. In practice, the gap is not a direct count of absent particles; it is a derived value that supports more comprehensive assessment of the patient’s chemistry profile.
When the body accumulates acids, bicarbonate is consumed and the gap may rise. That is why the anion gap calculator is often used as a quick medical reference during evaluation of a possible acid-base problem. A typical or unusual result can guide the next steps, but it should always be interpreted alongside the patient’s symptoms, blood gas findings, and other measured electrolytes.
Because the calculation is based on common lab values, it can be useful as a preliminary step in a wide range of settings. It does not replace a full evaluation, but it often helps narrow the cause of an abnormal blood gas or a suspicious electrolyte panel.
Anion Gap Formula Using Sodium, Potassium, Chloride, and Bicarbonate
The traditional formula includes sodium, potassium, chloride, and bicarbonate:
Anion gap = (Sodium + Potassium) − (Chloride + Bicarbonate)
Some formulas leave out potassium and use:
Anion gap = Sodium − (Chloride + Bicarbonate)
Both formulas are used in clinical practice. Including potassium makes the numerical result slightly higher, but many clinicians prefer the simpler version because potassium contributes less to the total and may not significantly change the decision-making process. What matters is knowing which formula your lab or clinician uses before comparing the result to a reference range.
Here is how each component contributes:
- Sodium serves as the main measured cation in the calculation. Potassium is a lesser measured cation that may be included in some formulas. Chloride is the primary measured anion that often rises when bicarbonate falls. Bicarbonate indicates buffer status and is central to interpreting acid-base balance.
The interplay of these values helps identify an anion difference that suggests acid retention, bicarbonate loss, or shifts in measured electrolytes. A proper calculation depends on reliable sodium level, potassium level, chloride level, and serum bicarbonate results from the same sample whenever possible.
How to Work With an Anion Gap Calculator Step by Step
An anion gap calculator makes easier the task, but the logic behind it is important. Use these steps for accurate use:
- Collect the lab values from a new serum chemistry or electrolyte panel. Make sure the sodium, potassium, chloride, and bicarbonate values are in the appropriate units used by the calculator. Input the measured electrolytes into the calculator accurately. Examine the calculated value and contrast it with the lab’s reference range or local normal values. Determine whether the result fits the clinical context, such as suspected metabolic acidosis or another acid-base disorder.
A useful way to think about it is that the calculator handles the arithmetic, but you supply the interpretation. For instance, a low serum bicarbonate with a high gap often suggests acid accumulation, while a low bicarbonate with a normal gap may point toward bicarbonate loss or another cause of non-gap acidosis.
It also helps to look for for consistency across related results. If one lab result looks abnormal, perform again testing or verify with a broader metabolic panel, especially when the numbers do not fit the patient’s condition. That is because a single abnormal result may reflect a specimen problem rather than a true physiologic change.
Expected Anion Gap Range and What Unexpected Results Mean
The typical anion gap typically falls within a laboratory-specific benchmark range, and the exact cutoff depends on whether potassium is included and how the analyzer reports bicarbonate and chloride. In most settings, the standard range is fairly narrow, but your local laboratory may define slightly different normal values.
A increased anion gap means there are additional unmeasured acids or unmeasured ions than expected. A reduced anion gap is less common and often points to albumin-related effects, excess positively charged proteins, or a testing problem. A negative value is atypical and should prompt a careful review for artifact or calculation issues.
Interpretation should focus on trends and context. A single abnormal result does not automatically confirm disease, but it can be an valuable clue when paired with symptoms, blood gas findings, kidney function, and the rest of the electrolyte panel. In other words, the gap is a clue, not a diagnosis.
Reasons of High Anion Gap Metabolic Acidosis
A high anion gap is usually associated with metabolic acidosis, which occurs when acids build up or when the body fails to clear them effectively. The most common causes include lactic acidosis, ketone-related acidosis, and impaired kidney function. These conditions increase the amount of acid in the bloodstream, reducing bicarbonate and increasing the gap.
Lactate buildup can occur when tissues are underperfused or oxygen delivery is inadequate, leading to excess lactate production. Ketoacidosis may develop in diabetes, starvation, or alcohol-related illness when ketone bodies accumulate. Impaired kidney function reduces the kidneys’ ability to excrete acid, allowing unmeasured acids to rise.
Other causes of increased gap metabolic acidosis include toxin exposure and certain inborn metabolic conditions, but those are beyond the core calculation itself. The important point is that a high Click here for info result indicates an acid-base disorder that often requires prompt workup. In that setting, the calculator supports early recognition, but the underlying cause still needs investigation.
When the gap is elevated, clinicians may also consider whether the bicarbonate is low enough to explain the change or whether a mixed disorder is present. That is where the delta ratio can become helpful, especially if the pattern suggests more than one process at the same time.
Reasons of Low Anion Gap
A reduced anion gap is not as common than a high one, but it can be clinically meaningful. A single of the most important causes is hypoalbuminemia, since albumin is a key anion-rich protein in the blood. Once albumin falls, the measured gap may also drop even if the patient has a real acid-base problem.
Further causes include hypercalcemia, which can shift the balance of measured cations and anion gap in chronic kidney disease anions, and multiple myeloma, where abnormal proteins may disrupt the charge balance. In some cases, laboratory error or sample contamination creates a falsely low or negative result. That is why unexpected values should be confirmed before being overinterpreted.
If the result is surprisingly low, review the full electrolyte panel, the clinical situation, and whether the patient has low albumin or a paraproteinemia. A low gap does not rule out illness; it can simply signal a different pattern of chemistry that needs a more detailed assessment.
Modified Anion Gap and Albumin Adjustment
Blood albumin significantly impacts the anion gap because albumin adds to the normal pool of unmeasured anions. When albumin is low, the measured gap may appear spuriously normal or low. That is why many clinicians use a corrected anion gap to account for hypoalbuminemia.
The corrected value helps distinguish a true acid-base abnormality from a protein-related shift. This is especially important in patients with chronic illness, malnutrition, liver disease, or other conditions that reduce albumin. Without correction, a hidden high gap metabolic acidosis may be missed.
Albumin adjustment is not just a math exercise. It reflects the role of protein binding in maintaining electrical neutrality. Because albumin is a major negatively charged protein, less albumin means fewer unmeasured anions in the baseline calculation. The corrected value therefore gives a better picture of the patient’s acid-base status.
In practical use, if albumin is below normal, the corrected value should be considered alongside the uncorrected result. That is often the most useful way to interpret an abnormal or borderline lab result, especially when the serum chemistry and blood gas do not seem to match.
Reading the Results and Frequent Calculation Errors
Good interpretation requires not just entering numbers. Several common issues can distort the result:
- Applying a different formula than the one the lab expects. Combining results from different collection times instead of using one sample. Overlooking albumin when a corrected value is needed. Overlooking a delta gap that suggests a mixed disorder. Overlooking measurement error or specimen issues in the electrolyte panel.
The delta gap is especially useful when a high gap is present. It compares the change in anion gap to the drop in bicarbonate and may reveal a second acid-base disorder masked beneath the first. This matters when the pattern does not fit a simple picture of metabolic acidosis.
It is additionally important to note that the calculator is only as accurate as the entered electrolytes input into it. If sodium, chloride, or bicarbonate values are inaccurate, the final calculated value will also be misleading. For that reason, an unexpected abnormal result should prompt a review of the specimen and the broader electrolyte panel.
A useful approach is to ask three questions: Does the number fit the clinical picture? Could hypoalbuminemia explain the gap? Is there any reason to suspect laboratory error or another preanalytic issue? These questions often improve clinical interpretation more than the arithmetic alone.
When to Use the Anion Gap in Clinical Practice
The anion gap is commonly used when reviewing a metabolic panel or broader blood chemistry profile. It is especially helpful during emergency evaluation of patients with altered mental status, dehydration, suspected poisoning, severe infection, kidney dysfunction, or unexplained tachypnea. In each of these settings, the gap can provide a fast clue about acid accumulation.
In a typical diagnostic workflow, clinicians first review the serum bicarbonate, chloride level, sodium level, and potassium level, then calculate the gap and assess whether the patient has a normal gap, high gap, or low gap pattern. From there, they decide whether to order further testing, such as lactate, ketones, kidney function studies, or albumin.
This makes the calculator useful as a screening step, but not a standalone answer. It is best viewed as one part of a larger evaluation that includes history, physical examination, blood gas testing, and follow-up labs. Used this way, it becomes a dependable guide for identifying an acid-base disorder early.
Frequently Asked Questions
How do you calculate the anion gap with sodium, potassium, chloride, and bicarbonate?
Use the formula: anion gap = (sodium + potassium) − (chloride + bicarbonate). Some clinicians omit potassium and use sodium − (chloride + bicarbonate). The key is to use the same formula consistently when comparing results and to confirm which version your lab or medical reference uses.
What’s a normal anion gap value?
A typical anion gap depends on the formula used and the laboratory’s reference range. The potassium-including formula is usually slightly higher than the version without potassium. You should always interpret the result using the local normal values reported with the electrolyte panel rather than relying on a single universal cutoff.
Why is potassium sometimes included in the anion gap formula?
Potassium is sometimes included because it is one of the measured electrolytes and helps determine the overall charge balance. However, its effect is relatively small compared with sodium, chloride, and bicarbonate. Many clinicians omit it for simplicity, but either method can be valid if used consistently.
What can a high anion gap mean?
A high anion gap usually suggests metabolic acidosis caused by accumulation of unmeasured anions, such as in lactic acidosis, ketoacidosis, or renal failure. It can also reflect other acid-base disorders or mixed conditions. The result should be interpreted with serum bicarbonate, blood gas findings, and the clinical context.
Does low albumin alter the anion gap result?
Yes. Low albumin can lower the measured anion gap because serum albumin is a major unmeasured anion. In hypoalbuminemia, the corrected anion gap may reveal an abnormality that the uncorrected value hides. For this reason albumin adjustment is important when the result does not match the patient’s condition.