What does the anion gap mean?
The anion gap is a calculated value used to evaluate acid-base balance from a routine electrolyte panel or serum chemistry. It evaluates major measured cations and anions, typically using sodium, chloride, and bicarbonate. Because not all charged particles are directly measured, the anion gap suggests the amount of unmeasured anions in the blood.
In its standard form, the calculation is:
Anion gap = sodium anion gap in chronic kidney disease - (chloride + bicarbonate)
Some formulas include potassium, but many clinicians use the basic version without it because potassium contributes less to the final value. The key idea is that a rising gap can suggest a metabolic derangement caused by acids or other unmeasured substances.
Understanding the anion gap normal range matters because a value that looks “normal” may still be misleading if albumin is low or if there are mixed disorders. That is why interpretation should always happen in clinical context, not in isolation.
Why sepsis alters the anion gap
Sepsis can affect the anion gap because it often causes metabolic acidosis, especially when oxygen delivery and utilization are reduced. In a shock state, tissues may not receive enough oxygen, leading to tissue hypoperfusion and increased anaerobic metabolism. This can raise acid production, especially lactic acidosis, which raises the gap.
When cells generate excess lactate, hydrogen ions accumulate and bicarbonate is consumed buffering the acid. The result is often a lower bicarbonate level and an anion gap elevation. In sepsis, this pattern is a useful diagnostic clue because it may reflect occult hypoperfusion even before blood pressure becomes severely abnormal.
Sepsis also produces a broader inflammatory and metabolic response that can contribute to organ dysfunction. Kidney involvement, altered perfusion, and changes in acid handling may all influence the gap. In other words, the anion gap is not just about lactate; it is a window into the biochemical effects of critical illness.
How to calculate and correct the anion gap
You can determine the anion gap manually, but an anion gap calculator is often helpful for fast analysis and for minimizing arithmetic errors. The calculator typically uses sodium, chloride, and bicarbonate, and some tools allow you to include potassium. Even so, the number should always be considered alongside the patient’s overall acid base picture.
One of the most important modifications is the corrected anion gap, also called the albumin-corrected gap. Because albumin is a major unmeasured anion, low albumin can make the gap appear spuriously low or “normal.” In sepsis, hypoalbuminemia is frequent, so the uncorrected value may miss the true burden of acids.
A practical approach is to:
- Check the sodium, chloride, and bicarbonate values from the chemistry panel. Compute the anion gap using a consistent formula. Check albumin and consider an albumin-corrected gap if it is low. Compare the result with the blood gas and serum lactate.
Correction does not replace clinical judgment. It simply increases accuracy when assessing whether the patient has hidden acid accumulation. In septic patients, this step can reduce the risk of a missed diagnosis of ongoing acid generation.
Elevated anion gap compared with expected-range anion gap in sepsis
With sepsis, a high anion gap metabolic acidosis often points to accumulation of organic acids, especially lactate. This is the usual pattern when tissue oxygen delivery is impaired. Still, sepsis can also present with normal anion gap metabolic acidosis, particularly when bicarbonate is lost or when chloride rises relative to bicarbonate after large-volume fluid resuscitation.
This difference matters because a normal gap does not rule out significant illness. A patient may still have acidemia, elevated lactate, or impaired perfusion even if the calculated gap stays within the expected range. Mixed disorders are common in critical https://anion-gap-checker101.scriblorax.com/posts/anion-gap-calculator-for-children-how-to-interpret-results illness, so a “normal” result may mask concurrent problems.
Lactate is often the leading driver of a high gap in sepsis, but it is not the only one. If the patient has kidney injury, acids can accumulate because renal clearance is reduced. This can further increase the gap or complicate the pattern seen on the blood gas.
It helps to think the anion gap as a clue to the type of acidosis:
- High anion gap metabolic acidosis suggests unmeasured acids such as lactate or ketones. Normal anion gap metabolic acidosis suggests bicarbonate loss, chloride gain, or mixed physiology.
With sepsis, both patterns may occur over time as the patient’s perfusion, kidney function, and treatment response evolve.
Frequent causes of high anion gap among septic patients with sepsis
The primary cause of an increased gap in sepsis is lactate from lactate-related acidosis. This may stem from reduced tissue blood flow, microcirculatory dysfunction, or impaired oxygen utilization. But an elevated anion gap should not be assumed to be lactate alone.
Other important causes include:
- Diabetic ketoacidosis, especially when the patient has diabetes, poor intake, or severe stress physiology. Renal failure, which reduces acid excretion and allows unmeasured anions to accumulate. Poisonous alcohols, such as methanol or ethylene glycol, which are less common but high-risk and should be considered when the story does not fit sepsis alone.
These other causes matter because sepsis can coexist with other metabolic problems. A patient may have infection plus ketoacidosis, or sepsis plus renal failure. The gap should prompt a broader differential rather than a single-track conclusion.
If the anion gap is rising and lactate is not very high, clinicians should consider whether another process is contributing. This is one reason serial assessment is more useful than a single isolated number.
Clinical interpretation: what the result reveals and misses
The anion gap is best used as a diagnostic clue, not a standalone diagnosis. It can point to the presence of an acid–base imbalance, but it does not determine the exact cause by itself. In sepsis, this is especially important because more than one process may be happening simultaneously.
A high gap may indicate accumulating unmeasured acids, but the number alone cannot tell you whether the cause is lactate, ketoacidosis, renal failure, or a toxin. Likewise, a normal gap does not exclude clinically important illness. That is why the anion gap must be paired with a blood gas, serum lactate, kidney function, and the overall exam.
One useful way to read the number is to ask three questions:
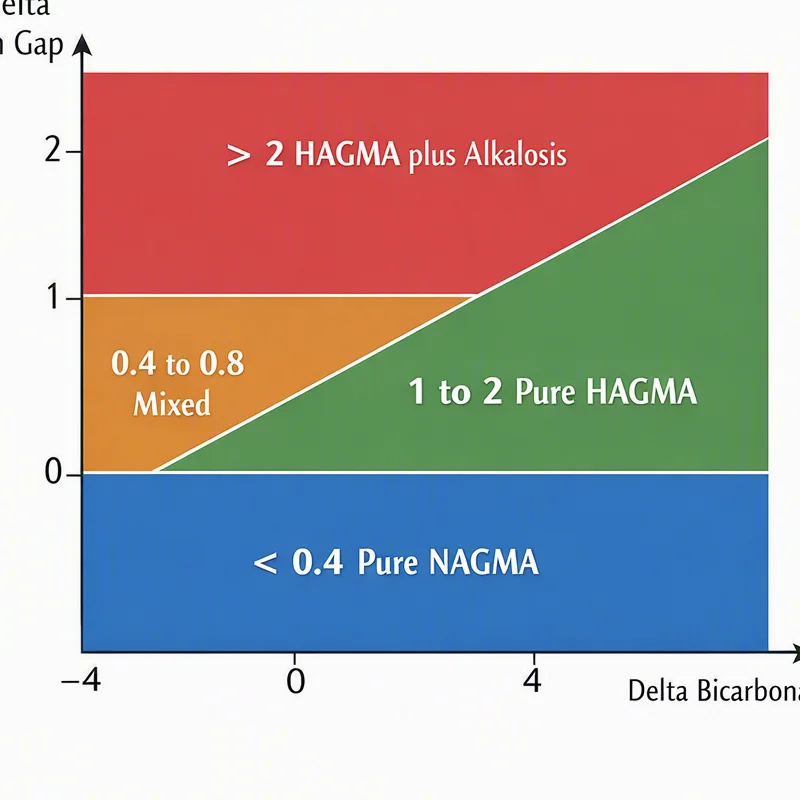
- Is there acidemic change on the blood gas? Is the calculated gap elevated after considering albumin? Does the pattern fit the patient’s presenting situation and perfusion status?
If the answer is yes to all three, the concern for clinically significant acid accumulation is higher. If there is a mismatch, evaluate mixed acid-base disease, laboratory timing issues, or a non-lactate cause of metabolic derangement.
In short, the number does not replace bedside assessment. It reinforces or undermines a hypothesis about what is happening physiologically.
When to recheck labs and judge severity
For patients with sepsis, serial testing is often more useful than one isolated measurement. Lactate over time levels help reveal whether the patient is clearing lactate or ongoing lactate production is present. Likewise, repeating the electrolyte panel can demonstrate whether the anion gap is getting better, stable, or worsening.
Providers also assess the base deficit on the blood gas as an additional marker of metabolic burden. A worsening base deficit may support ongoing acidosis even if the gap has not yet shifted much. Together, these values can help with assessing severity and therapeutic response.
Repeat labs are especially useful when:
- The initial lactate is elevated and you want to follow lactate clearance. There is worry for persistent perfusion problems. There is declining organ function or suspected renal impairment. The first anion gap and blood gas do not align with the clinical picture.
Trending the numbers can uncover improving perfusion after resuscitation or an occult decline that requires escalation. In critical illness, the pattern often is more important than the single value.
FAQs about anion gap in sepsis
What does anion gap tell you in sepsis?
In sepsis, the anion gap helps identify whether there is a metabolic acidosis with unmeasured acids in blood. An elevated gap can suggest lactic acidosis from tissue hypoperfusion, but it may also reflect ketoacidosis, renal failure, or toxic alcohol exposure. It is a useful clue, not a standalone diagnosis.
Can sepsis lead to a normal anion gap?
Yes, it can. Sepsis can cause a normal anion gap metabolic acidosis, especially when bicarbonate is lost or chloride rises during fluid treatment. A normal anion gap does not rule out serious illness, elevated lactate, or poor perfusion. Mixed acid-base disorders are common in sepsis.
Why is it important to correct the anion gap for albumin?
Albumin is a major unmeasured anion, so low albumin can make the measured anion gap look deceptively normal. Correcting for albumin gives a more accurate picture of the true acid burden. This is especially important in critical illness, where hypoalbuminemia is common.
Does a high anion gap always mean lactic acidosis in sepsis?
No, it does not. Lactic acidosis is common, but a high anion gap can also come from ketoacidosis, renal failure, or toxic alcohols. The anion gap should always be interpreted with the blood gas, serum lactate, albumin, and the rest of the clinical context.
When should an anion gap be repeated in a septic patient?
Repeat it when you are monitoring response to treatment, especially if lactate is elevated, perfusion is uncertain, or the patient’s condition is changing. Trending the anion gap with serial lactate, electrolytes, and base deficit helps show whether the metabolic derangement is improving or worsening.